Steps in Protocol Development and Training
What You Will Learn in This Chapter
Every neurofeedback session starts with the same practical question: where do I put the electrodes, and what do I train? This unit gives you a systematic way to answer it. You will learn how to check for functional causes that may be driving a client's symptoms, how to weigh the factors that guide protocol selection, and how to use an evidence-based decision process that combines neuroscience research with good clinical reasoning.
You will also follow detailed case examples from assessment through protocol selection, training, and reassessment, so you can see how the framework works with real clients. Throughout the unit, neurofeedback is presented as what it is: training. The client is actively learning self-regulation skills, and the practitioner is the trainer and coach.
BCIA Blueprint Coverage: This unit addresses VII. Developing Treatment Protocols - B. Steps in protocol development and treatment planning using one or more of the treatment models (Blueprint Code VII-B).
Learning Objectives
After completing this section, you will be able to:
Identify red flags that should trigger a functional or integrative medicine consultation before starting neurofeedback.
Describe the key factors to consider when selecting neurofeedback training protocols, including client condition, research findings, practitioner expertise, resources, environmental context, and client values.
Explain how an arousal model can guide the classification of client presentations and protocol selection.
Apply an evidence-based decision-making flowchart to match client problems with appropriate neurofeedback protocols.
Interpret qEEG assessment findings and translate them into training protocol recommendations through case example analysis.
Explain why neurofeedback is best understood as training rather than treatment, and describe the learning principles and research-supported steps of a neurofeedback training process.
Overview
This section covers four topics: when to pause and look for functional causes before starting neurofeedback, the factors that shape protocol selection, a decision-making flowchart you can use in practice, and the learning principles and practical steps that turn a protocol into an effective course of training. Think of all this as a starting point for clinical reasoning, not a recipe. Whatever protocol you choose, you should be able to explain why you chose it.
We begin with a question that may surprise you. Should you start neurofeedback at all? In difficult cases the answer may be "not yet." Some clients have symptoms with functional causes, such as environmental exposures, infections, or metabolic imbalances, that call for blood and urine testing before training can be effective.
Dr. Ron Swatzyna and colleagues (2024) urge clinicians to think beyond DSM-5 diagnoses. They advocate collaborating with neurologists and functional and integrative medicine professionals to uncover the root causes of a client's complaints before beginning biofeedback or neurofeedback. This represents a paradigm shift: rather than addressing only the symptoms that appear in the EEG, you investigate what might be driving those symptoms in the first place.
What are the "red flags" that should trigger a functional or integrative medicine consult? The first red flag is that symptoms such as hyperactivity or tics are new or have worsened dramatically (R. J. Swatzyna, personal communication to Fred Shaffer, August 9, 2024). The second involves abnormal EEG amplitude and peak frequency values. For example, a low-amplitude 6.5-Hz peak frequency in a 10-year-old is not age-appropriate and should be investigated; a series of EEGs can reveal whether the pattern is worsening over time (R. J. Swatzyna, personal communication to Fred Shaffer, August 9, 2024).
The third red flag appears when a neurologist confirms biomarkers in the raw EEG. These include focal slowing (FS), meaning slower-than-normal brainwave activity localized to a specific brain region; spindling excessive beta (SEB), abnormal bursts of beta activity that appear as spindles and may indicate cortical irritability; encephalopathy (EN), or widespread brain dysfunction; and isolated epileptiform discharges (IEDs), brief abnormal electrical bursts that can signal cortical irritability even in non-epileptic individuals. These biomarkers may point to underlying physiological processes like neuroinflammation. Collaborating with a board-certified neurologist can sharpen your raw EEG interpretation and strengthen your credibility with the client's physician (Swatzyna et al., 2024).
Swatzyna et al. (2024, p. 9) describe EEG biomarker identification as a positive step toward personalized medicine: by recording directly from the brain, practitioners gain a deeper understanding of the underlying brain activity and can tailor plans to the specific needs of each client.
When red flags point to possible environmental causes such as lead or mold exposure, or to gut-brain dysfunction, you can recommend that your client consult with a functional or integrative medicine professional in your area. That specialist will determine which tests are needed based on the client's symptoms, medical history, and EEG findings. Crucially, you should not begin biofeedback and neurofeedback until suspected causes are ruled out or medically addressed, which might mean waiting several months for gut-wall repair in cases of dysbiosis or for a mold detox protocol to reduce mycotoxin levels.

This paradigm shift might feel overwhelming, but it doesn't have to be if you "stay in your lane." Your role is to do what you already do best: identify red flags and make referrals when needed. The functional and integrative medicine professionals will decide which tests to order, interpret the results, and recommend evidence-based medical interventions (R. J. Swatzyna, personal communication to Fred Shaffer, August 9, 2024). Collaboration, not reinvention, is what this shift requires.
Swatzyna and colleagues (2024) encourage clinicians to look beyond DSM-5 diagnoses and partner with neurologists and functional medicine professionals. Three red flags should prompt referral: new or dramatically worsening symptoms, abnormal EEG amplitude and peak frequency values, and the presence of raw EEG biomarkers such as focal slowing, spindling excessive beta, encephalopathy, and isolated epileptiform discharges. Swatzyna advises against beginning neurofeedback until suspected functional causes have been ruled out or addressed (R. J. Swatzyna, personal communication to Fred Shaffer, August 9, 2024).
Clinical Examples
The following twelve cases were contributed by a diverse group of medical professionals. They are uncontrolled clinical vignettes reported by the attending clinicians rather than published case studies, so read the outcomes as illustrations of a reasoning process rather than as evidence that the identified cause produced the symptoms. In this section, you will see how functional causes, ranging from mold exposure to nutrient deficiencies, can masquerade as psychiatric diagnoses. In each case, the attending clinician judged that addressing the DSM-5 diagnosis alone with medication and neurofeedback would have missed the underlying problem.
Case Example 1: Mold Exposure and Cognitive Decline. A 40-year-old woman presented with depression, anxiety, and cognitive decline. Antidepressants provided only partial relief. A functional medicine assessment uncovered significant mold exposure in her home, and testing confirmed the presence of mycotoxins, toxic compounds produced by mold, in her body.
Her care plan involved remediating her home, detoxification protocols to eliminate mycotoxins, and support for her immune system and gut health. As the toxins cleared, her psychological symptoms improved dramatically and her cognitive function returned to normal. This case illustrates why addressing the root cause, mold toxicity, was essential before any self-regulation training could be effective.
Case Example 2: Glyphosate Exposure and ADHD. A 10-year-old boy diagnosed with ADHD was prescribed stimulant medication. While helpful for symptom management, the medication caused insomnia and decreased appetite. A functional medicine practitioner explored environmental factors and discovered that the family lived near agricultural fields regularly sprayed with glyphosate, a widely used herbicide with potential neurotoxic effects. Testing revealed high glyphosate levels in the boy's system.
The medical plan included dietary changes to support detoxification, nutritional supplementation for brain health, and measures to reduce ongoing glyphosate exposure. As his glyphosate levels dropped, his ADHD symptoms improved and he was able to reduce his reliance on stimulant medication.
Case Example 3: Chronic Inflammatory Response Syndrome (CIRS). A 35-year-old man experienced severe fatigue, brain fog, and mood swings. Despite seeing multiple specialists and trying various medications, his symptoms persisted. A functional medicine assessment raised chronic inflammatory response syndrome (CIRS), a proposed condition attributed to biotoxin exposure and said to produce chronic inflammation and multi-system symptoms, though it appears in neither the DSM nor the ICD and its evidence base is disputed. Advanced testing confirmed elevated inflammatory markers and biotoxin levels, likely from water-damaged buildings.
Medical care involved detoxification protocols, binders to remove biotoxins, and immune and nervous system support. Addressing the biotoxin exposure and inflammation led to significant improvements in energy, cognitive function, and mood, underscoring the importance of identifying root causes in cases that have not responded to prior interventions.
Case Example 4: Lyme Disease and Psychiatric Symptoms. A 28-year-old woman presented with severe anxiety, depression, and panic attacks. Antidepressants and anxiolytics provided minimal relief. A functional medicine practitioner considered the possibility of underlying infections and ordered comprehensive testing, which revealed Lyme disease and co-infections, a finding that reframed her psychiatric symptoms as consequences of a correctable medical condition.
Her medical care included antimicrobial therapies to address the infections, immune support, and anti-inflammatory interventions. As the infections came under control, her psychiatric symptoms began to resolve. This case powerfully demonstrates the need to investigate underlying medical conditions rather than addressing symptoms in isolation.
Case Example 5: Addison's Disease and Depression. A 45-year-old man was experiencing severe fatigue, weight loss, and depression. Antidepressants and therapy had little effect. A functional medicine practitioner discovered Addison's disease, a condition in which the adrenal glands produce insufficient cortisol. Because cortisol regulates energy, mood, and stress response, this deficiency was directly driving his psychological symptoms.
Hormone replacement therapy corrected the cortisol deficiency, supplemented by measures to strengthen his overall health. Once the Addison's disease was managed, his depression and fatigue improved markedly. This case illustrates how an endocrine disorder can mimic a primary psychiatric condition.
Case Example 6: Environmental Toxins and New OCD Symptoms. A 22-year-old woman developed new-onset obsessive-compulsive disorder (OCD) symptoms, including severe anxiety and compulsive behaviors. Psychiatric medications provided minimal relief. A detailed environmental assessment revealed high-level exposure to volatile organic compounds (VOCs) in her workplace, and testing confirmed elevated toxin levels in her body.
Her care focused on reducing VOC exposure, detoxification protocols, and nutritional support to enhance her body's toxin-elimination pathways. As her toxin burden decreased, her OCD symptoms and anxiety significantly improved, a reminder that new-onset psychiatric symptoms warrant investigation of environmental exposures.
Case Example 7: Tics and Heavy Metal Toxicity. A 15-year-old boy developed motor tics and was diagnosed with a tic disorder. Behavioral therapy and medications were only partially effective. Comprehensive functional medicine testing revealed high levels of heavy metals, particularly lead, in his system, a likely contributor to his neurological symptoms.
The medical plan included chelation therapy to remove heavy metals, dietary modifications to support detoxification, and supplements to restore nutritional balance. As heavy metal levels decreased, the boy's tics diminished in frequency and severity. This case illustrates the importance of screening for environmental toxins when neurological symptoms resist standard interventions.
Case Example 8: PANS/PANDAS and Psychiatric Symptoms. A 12-year-old girl suddenly developed severe anxiety, obsessive-compulsive behaviors, and mood swings. Psychiatric interventions were ineffective. A functional medicine practitioner suspected Pediatric Acute-onset Neuropsychiatric Syndrome (PANS) or Pediatric Autoimmune Neuropsychiatric Disorders Associated with Streptococcal Infections (PANDAS), conditions in which infections trigger the immune system to attack the brain. Dr. Melissa Jones expects these terms to eventually be subsumed under the broader diagnosis of autoimmune encephalitis, which refers to brain inflammation caused by the body's own immune system.
Comprehensive testing confirmed a recent streptococcal infection and elevated autoimmune markers. Medical care included antibiotics, anti-inflammatory therapies, and immune-modulating therapies. As the underlying infection and inflammation resolved, the girl's psychiatric symptoms improved significantly, highlighting the need for comprehensive workup when psychiatric symptoms appear suddenly in children.
Case Example 9: Autism and Gut Health. A 6-year-old boy diagnosed with autism spectrum disorder (ASD) exhibited severe gastrointestinal issues, including chronic diarrhea and abdominal pain. Behavioral interventions addressed his autism but did nothing for his physical discomfort. A functional medicine evaluation revealed significant dysbiosis, an imbalance in his gut microbiome, the vast community of microorganisms living in and on the human body, particularly in the digestive tract.
His care included a specialized diet to eliminate food sensitivities, probiotics to restore healthy gut flora, and anti-inflammatory supplements. As his gut health improved, notable enhancements appeared in his mood, behavior, and communication skills. This case demonstrates the profound impact that gut-brain axis health can have on ASD symptoms.
Case Example 10: Oppositional Defiant Disorder and Nutrient Deficiencies. An 8-year-old girl diagnosed with oppositional defiant disorder (ODD) was struggling with severe temper tantrums, defiance, and aggression. Behavioral therapy provided limited success. A functional medicine assessment revealed multiple nutrient deficiencies, including low levels of zinc, magnesium, and vitamin D, all of which play important roles in brain function and mood regulation.
Her care included dietary changes to ensure nutrient-rich meals and targeted supplementation. As her nutrient levels normalized over time, her behavior improved significantly. This case highlights how nutritional imbalances can masquerade as psychological and behavioral disorders.
Case Example 11: Strep Infection Leading to Tonsillectomy and Adenoidectomy. A 7-year-old girl developed sudden-onset obsessive-compulsive behaviors and tics. Standard psychiatric medications were ineffective for several weeks, prompting a functional medicine consultation. A detailed medical history revealed a recent bout of strep throat, and blood tests showed elevated anti-streptolysin O (ASO) titers, confirming a recent streptococcal infection.
Despite an initial course of antibiotics, her symptoms persisted, and recurrent strep infections were suspected. To eliminate the chronic infection source, a tonsillectomy and adenoidectomy were recommended. Post-surgery, she showed significant improvement in her neuropsychiatric symptoms. This case illustrates the importance of addressing persistent infection sources in pediatric autoimmune neuropsychiatric disorders associated with streptococcal infections.
Case Example 12: UTI-Related Dementia Symptoms in an Older Adult. An 82-year-old man experienced rapid cognitive decline and behavioral changes, initially diagnosed as dementia by his primary care physician. Symptoms included confusion, agitation, and memory loss that severely affected his quality of life. A functional medicine practitioner was consulted for a second opinion.
A thorough evaluation, including laboratory tests, identified a urinary tract infection (UTI) as the underlying cause of his symptoms. In older adults, UTIs can trigger delirium and dementia-like presentations due to systemic inflammation and infection. An appropriate course of antibiotics eradicated the infection, and his cognitive function improved markedly. This case underscores the necessity of considering infections and other reversible conditions when evaluating cognitive decline in older adults.
These twelve cases demonstrate that functional causes, including mold exposure, glyphosate toxicity, CIRS, Lyme disease, Addison's disease, environmental toxins, heavy metals, autoimmune encephalitis (PANS/PANDAS), gut dysbiosis, nutrient deficiencies, streptococcal infections, and UTIs, can produce psychiatric and neurological symptoms. In each, the attending clinician judged that addressing the DSM-5 diagnosis alone would have been insufficient. Because these are uncontrolled vignettes, they cannot establish how often such causes are present or how reliably addressing them resolves symptoms; what they do establish is that the possibility is worth ruling out. The common thread is the value of collaboration with functional and integrative medicine professionals in identifying and addressing underlying conditions before neurofeedback begins.
Zebras and Horses: Health Care Reasoning Cautions
In the late 1940s, the physician Theodore Woodward is reported to have taught his students, "When you hear hoofbeats behind you, don't expect to see a zebra," a maxim also remembered as "When you hear hoofbeats, think of horses, not zebras" (Smith & Paauw, 2000). The point for a practitioner assessing a client, their symptoms, and the possible root cause is to keep the base rate, the likelihood of a symptom or condition in the population you serve, in mind before reaching a conclusion that will drive medical care or training. A symptom's clinical significance depends not only on how well it fits a diagnosis but also on how common that diagnosis is before the symptom is observed (Jaeschke et al., 1994). Low base rates should reduce unwarranted diagnostic certainty; they should not lead clinicians to dismiss potentially serious symptoms (Hirsch, 2020).
"Horses" are common conditions, such as stress, that may produce a given symptom, such as headache. "Zebras" are uncommon conditions, such as giant cell arteritis, that produce the same symptom. With an awareness of the base rates in your clinic, you can follow a process of reasoning that recognizes red flags and potentially dangerous "can't miss" diagnoses without the costly error of jumping to unlikely ones.
During this reasoning process, it is important to stay alert to cognitive biases, the heuristics and thinking shortcuts that the psychologist and Nobel laureate Daniel Kahneman (2011) describes. These include anchoring (stubbornly holding to an initial diagnosis), overconfidence, availability (preferring evidence that is easy to obtain or recently encountered over evidence that is less accessible or more remote), and sunk costs (persisting on a false trail because of the effort and expense already invested). Clinicians, like most people, are subject to these and other sources of error.
The core takeaway when a client presents with a common symptom such as anxiety, depression, fatigue, deficient attention, or headache is to investigate low-probability diagnoses only as part of a disciplined process. That process begins with careful definition of the symptom and examination of its history and base rate. It then asks whether the symptom may be an atypical presentation of a common condition, considers the base rates of the possible underlying conditions, and builds a differential diagnosis that compares the most likely cause with the alternatives. Throughout, the clinician integrates multiple sources of diagnostic information while looking for converging evidence. The low-probability zebras are pursued when the potential harm of missing the diagnosis outweighs the cost of the investigation (Hirsch, 2020; Jaeschke et al., 1994; Smith & Paauw, 2000).
A Neurofeedback Decision-Making Framework
Once functional causes have been addressed or ruled out, training can begin. This section introduces the evidence-based framework that guides protocol selection. It shows how clinical outcome research, neuroscience, and brain-behavior relationships come together to answer two questions: where do the electrodes go, and what do we train?
John S. Anderson discusses the process of developing evidence-based training protocols. Video © J. S. Anderson.
The model used here is evidence-based in the fullest sense: it draws on research studies, clinical experience, neuroscience, and brain-behavior relationships to select training protocols. We are indebted to Michael and Lynda Thompson, who have long advocated that clinical outcome research and neuroscience should inform neurofeedback protocol development (e.g., Thompson & Thompson, 2015). Their influence is central to the approach presented in this unit.
This section is also consistent with John Anderson's NewQ assessment method. Abbreviated Q assessments can provide useful information about the client, help validate and explain their symptoms, and assist with protocol selection. Video © J. S. Anderson.
The basic building blocks of any neurofeedback training protocol include electrode location, EEG frequency to be trained, EEG parameters (e.g., amplitude, amplitude ratios, connectivity measures, symmetry, peak frequency), and the direction of training, whether the selected parameter is trained up or down. When using 19-channel LORETA training, additional protocol features come into play, including specific cortical structures, Brodmann areas (cytoarchitectural zones of the cerebral cortex distinguished by Nissl staining; Brodmann numbered them 1-52, and roughly 43-47 are delineated in the human map), and brain networks.

BCIA Blueprint Coverage
This unit covers VII. Developing Treatment Protocols - B. Steps in protocol development and treatment planning using one or more of the treatment models (Blueprint Code VII-B).

The remainder of this unit covers three main topics: Factors to Consider when selecting protocols, Decision-Making and Ongoing Problem-Solving during training, and a practical Flowchart that ties the process together.
Factors To Consider
This section looks at six factors that shape protocol selection: the client's condition, research findings, practitioner expertise, available resources, environmental context, and the client's own values and preferences. Each one adds a different piece of the puzzle. Weighed together, they produce a protocol tailored to the individual rather than a one-size-fits-all approach. Let's take them one at a time.
Client Condition and Goals
The initial assessment tells you what the client wants to achieve, whether there are symptoms to decrease, abilities to enhance, or both. Contributing to your understanding of the client's condition are their personal and health histories, professional reports, and test findings. As described in the Assessment section of Neurofeedback Tutor: Assessment and Training, relevant information comes from diverse sources: self-report, direct behavioral observation, cognitive tests, questionnaires, and reports from significant others such as a parent, teacher, or spouse. EEG assessment results are central, and peripheral psychophysiological findings are often considered as well.
Training goals operate at three levels of analysis. The first level is biological and identifies where to train and which EEG variable to target. For example, finding excess posterior beta activity in a client seeking anxiety reduction may suggest electrode placement at P4.
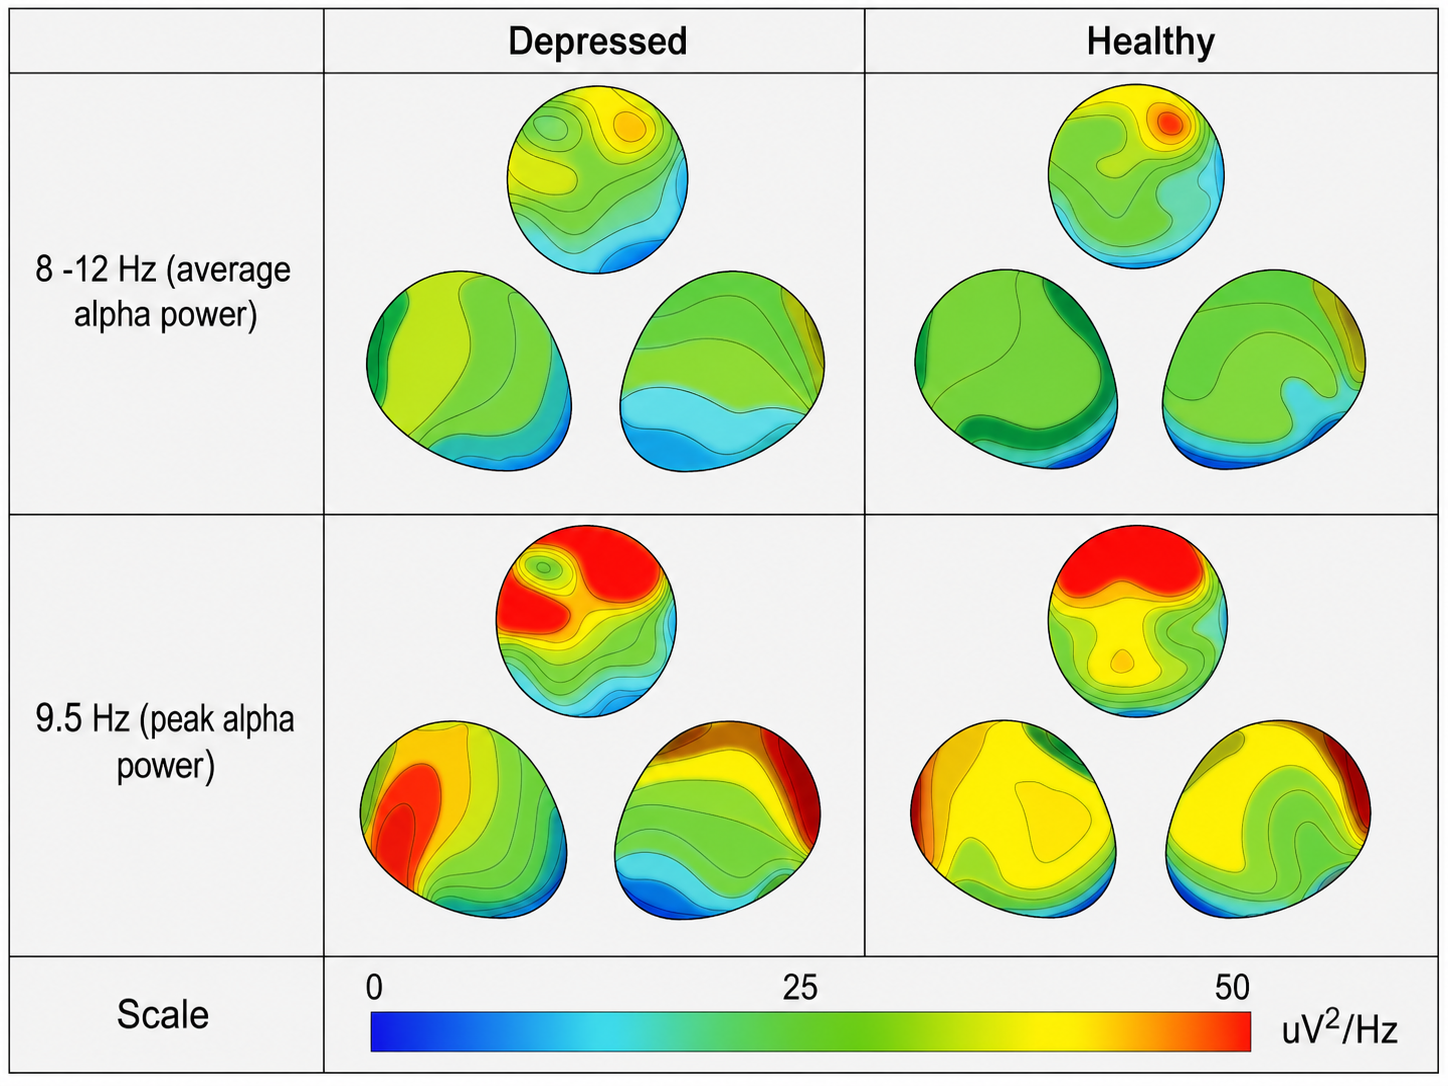
The second level is psychological, addressing the client's cognitive and emotional condition. If a client with depression shows prefrontal alpha asymmetry reversal, that is, greater alpha amplitude at F3 than at F4, this suggests placing electrodes at F3 and F4 and using an alpha asymmetry protocol. Gollan et al. (2014) found alpha asymmetry significantly higher in depressed than in healthy participants before therapy, but their study tested behavioral activation therapy rather than neurofeedback, and the asymmetry persisted after therapy whether or not clients remitted, so the pattern is better read as a marker identifying candidates for the protocol than as an index certain to normalize with recovery.
The third level concerns socially significant behavior change in a specific context. For example, a child with ADHD may show distractible behavior and poor grades in the classroom, deficient sustained attention, anxiety, and significantly excessive central theta EEG. A central bipolar electrode placement with a protocol rewarding sensorimotor rhythm (SMR), the 12-15 Hz spindle-shaped rhythm detected from the sensorimotor strip when individuals reduce attention to sensory input and motor activity, and favoring general alert attention, could improve both attention and academic performance.
Considering all three levels together within real-world contexts such as age-appropriate school, work, play, or social situations yields a holistic developmental biopsychosocial description of the client's condition. Combined with neuroscience research, this formulation explains why the client may have the symptoms they present and points toward where to place electrodes and what EEG variables to train.
Research Findings
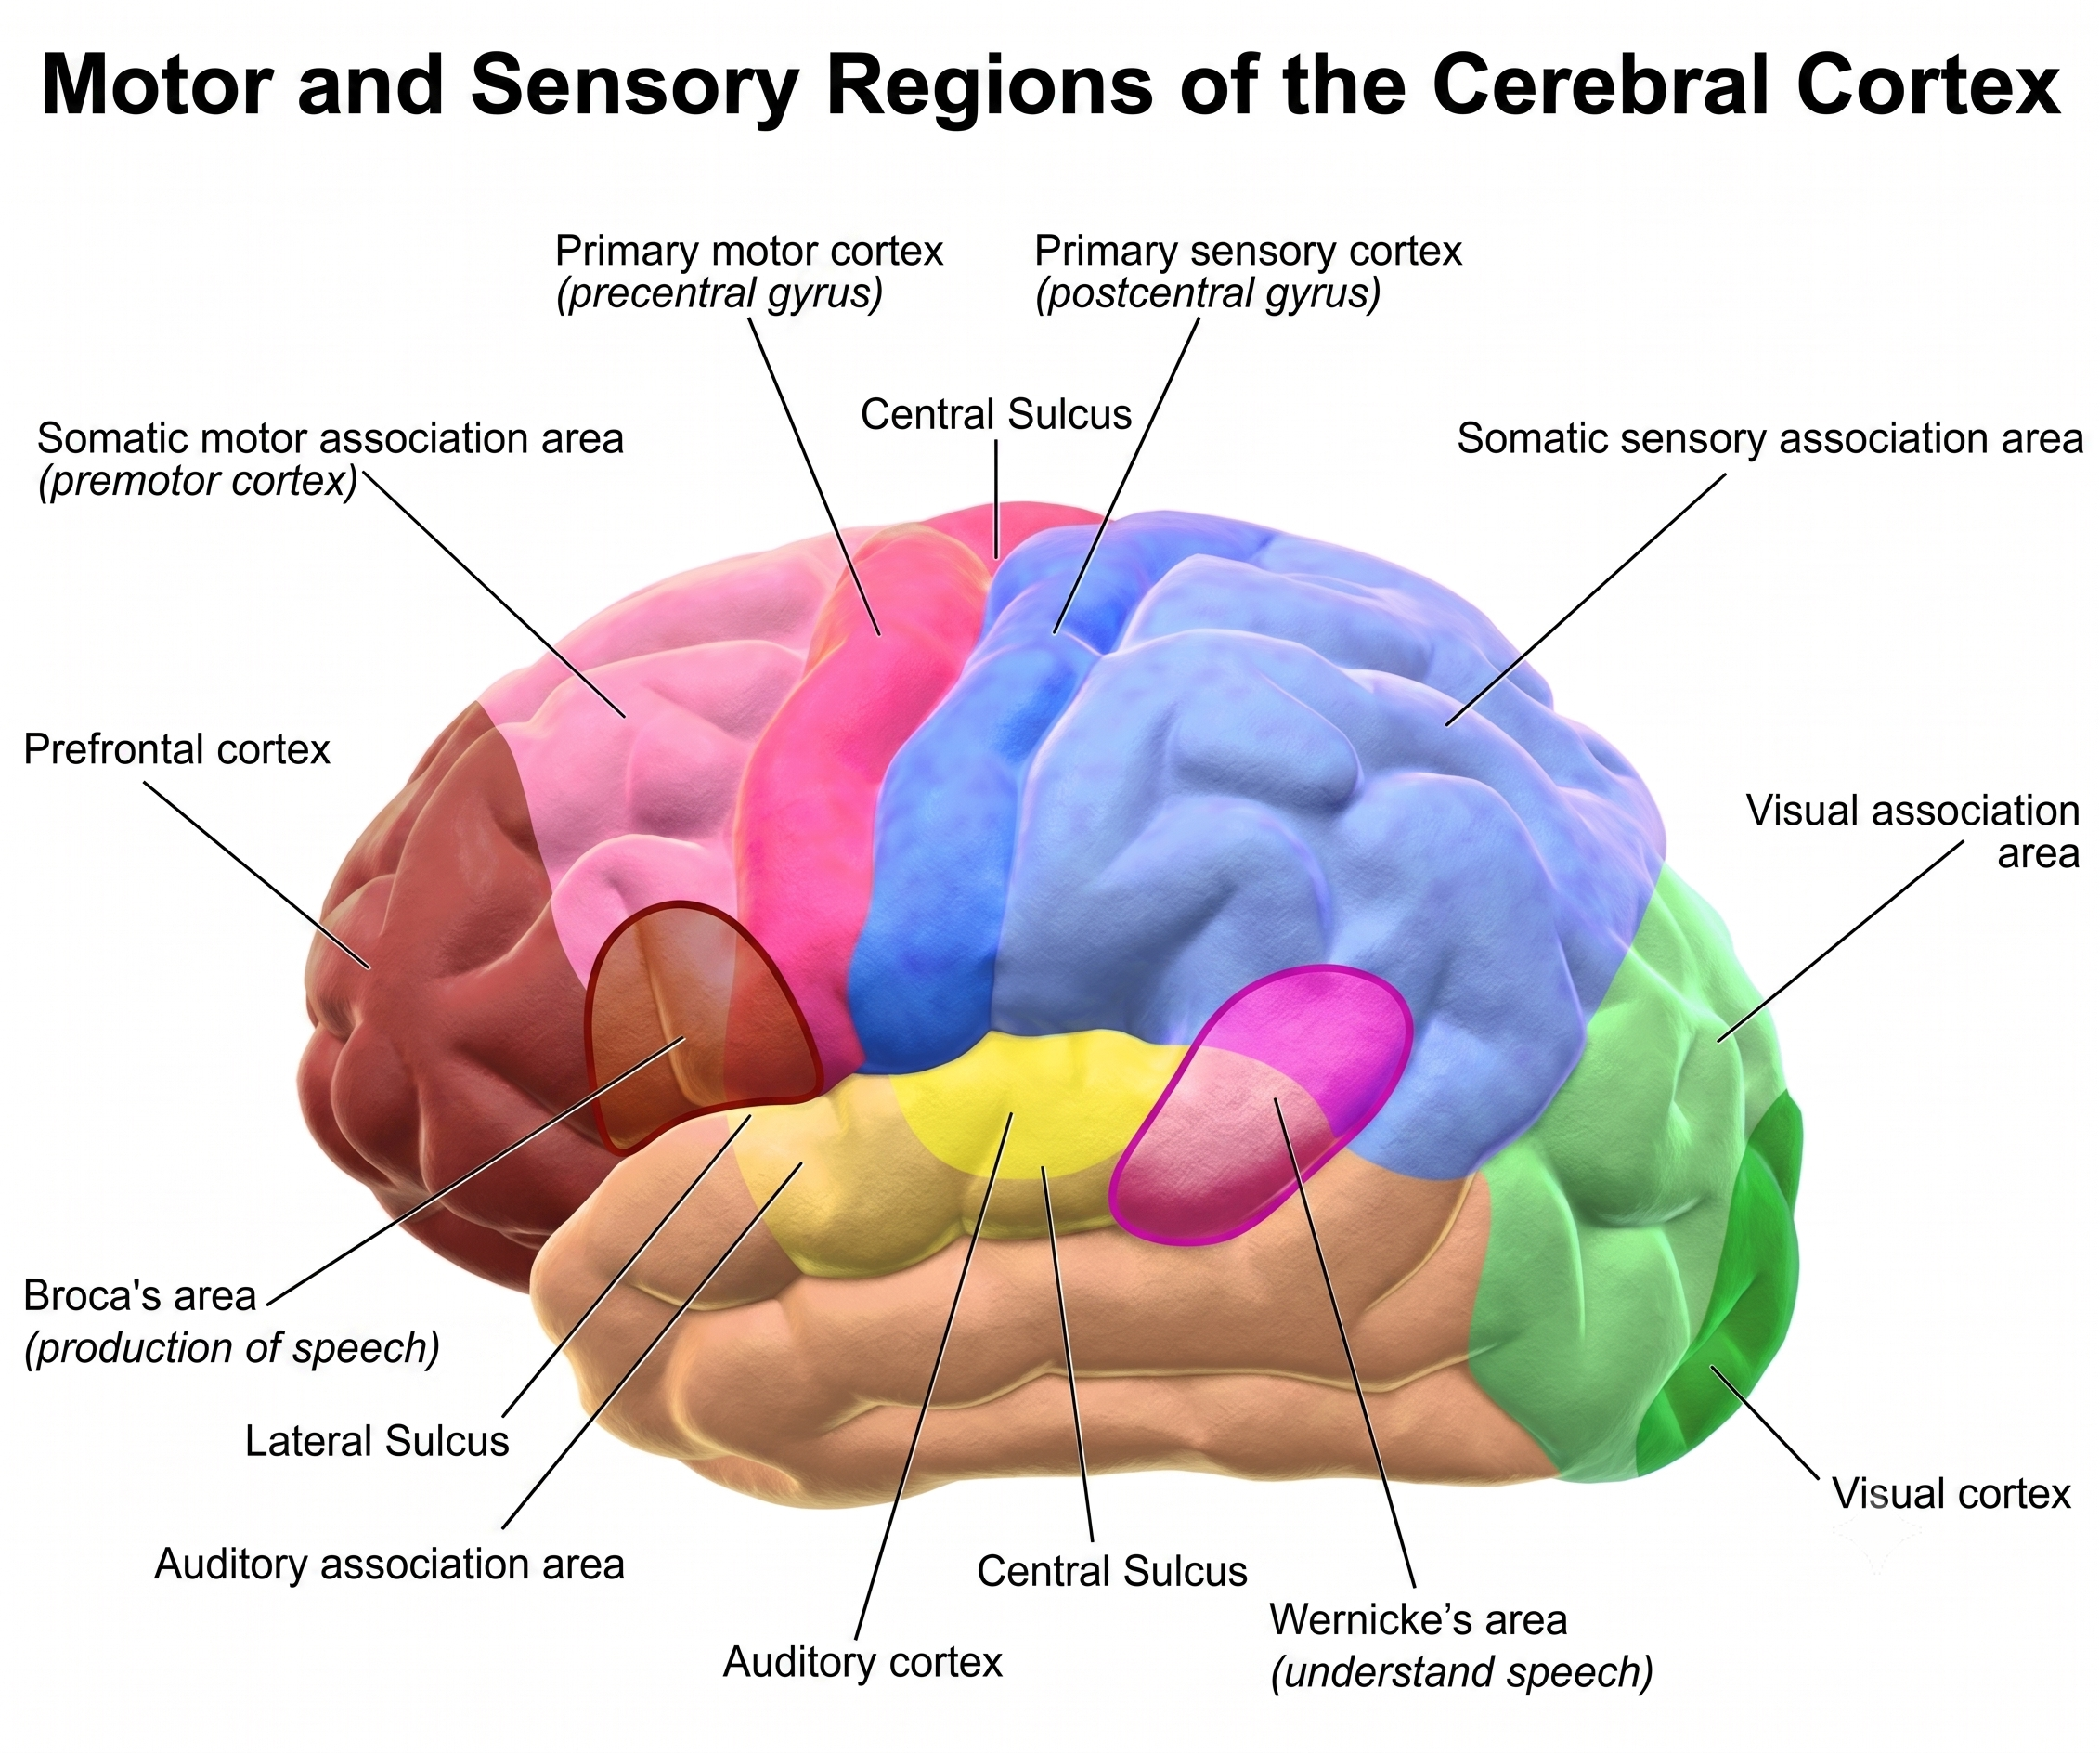
This section covers the four types of research findings that inform protocol selection: brain-behavior relationships, EEG correlates of clinical conditions, brain network anomalies, and neurofeedback efficacy studies. These layers of evidence build on one another: understanding how a function is affiliated with brain structures and their connections helps you interpret what the EEG is telling you, which in turn guides your choice of a research-supported protocol. One type of finding concerns brain-behavior relationships and functional neuroanatomy. For instance, language functions are a strength of the left hemisphere, and damage to the left temporal region may compromise language use.
A second type of research finding concerns the functional significance of EEG patterns and their correlation with specific conditions. For example, excess right frontal high beta (beta 4), 25-38 Hz activity mostly seen in the frontal lobes and associated with hyperarousal, has been linked to anxiety, as have beta spindling and excess posterior beta.
The video below is a 19-channel BioTrace+/NeXus-32 display of low beta and high beta activity. The 13-21 Hz and 22-34 Hz boundaries shown are the filter settings chosen for this display, not band definitions; this unit's glossary places beta 4 (high beta) at 25-38 Hz. Video © John S. Anderson. Brighter colors represent higher beta amplitudes, and frequency histograms are displayed for each channel.
Third, anomalies in brain networks are associated with various conditions and abilities. For example, dysfunction in the default mode network (DMN), a cortical network of frontal, temporal, and parietal regions most active during introspection and daydreaming and relatively quiet when we pursue external goals, has been linked to depression. Neurofeedback training can increase or decrease connectivity between brain sites using a normative database, which provides means and standard deviations for EEG variables calculated from healthy subjects grouped by age and condition. For example, BrainMaster's BrainAvatar software allows clinicians to train specific networks, like the DMN.
Finally, neurofeedback efficacy research is essential. For example, midline theta/beta training, a protocol that decreases theta amplitude and increases beta amplitude, has an established record of changing EEG patterns and of improving attention and classroom behavior in children with ADHD, though the largest double-blind randomized trial to date reported a null primary outcome (ICAN; Arnold et al., 2021). Knowing which protocols have research support gives you a defensible starting point for training.

Once you have described the client's condition and agreed on training goals, the next step is to evaluate how strongly the research supports any neurofeedback approach for similar goals. The Efficacy unit of Neurofeedback Tutor explained the scientific evidence levels and the varying evidence available for different protocols and conditions. For some conditions, such as ADHD, a substantial body of evidence addresses the efficacy and effectiveness of neurofeedback, though the strength of that evidence remains contested and blinded trials have been less favorable than open ones. Moreover, more than one method may show benefit: for ADHD, both theta/beta training and slow cortical potential (SCP) training along the midline have research support.
A useful strategy for protocol selection, as presented in the training protocol development video, is an arousal model that classifies client presentations as overaroused or underaroused. Research supports various protocols for each category. Electrode site and EEG training parameters can also be guided by functional neuroanatomy, that is, the function of the cortical tissue beneath an electrode site or within a Brodmann area. Researchers have revised the Brodmann maps and correlated specific areas with their functions, giving practitioners a neuroanatomical rationale for electrode placement.
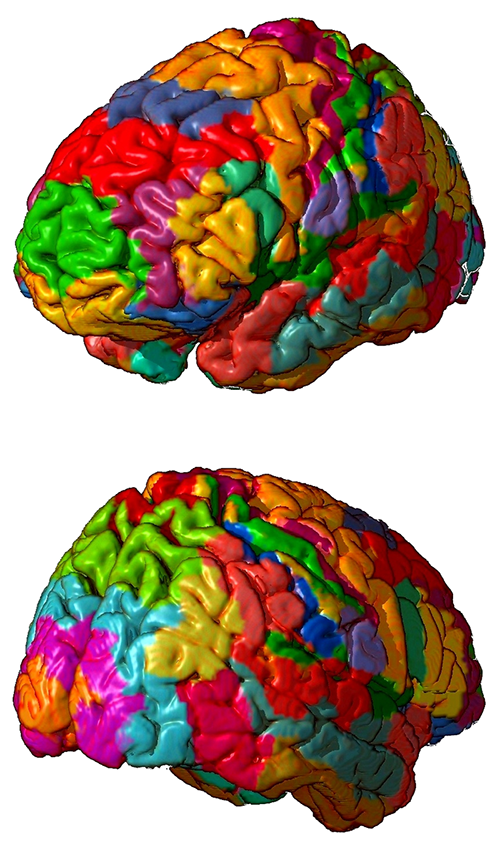
Protocol selection also draws on normative values of frequency bands at particular locations. Understanding whether excess EEG parameters represent overarousal or underarousal in a given area helps you determine which psychological or behavioral functions may be compromised. Robert Thatcher and his team have continued to develop the NeuroGuide database and the features of 19-channel z-score training, a strategy that attempts to normalize brain function relative to database means, most recently with the development of swLORETA, which improves on sLORETA by applying a singular-value-decomposition-based weighting of the lead field, making the solution more robust under noisy recording conditions and more sensitive to deep sources (Palmero-Soler et al., 2007). Both descend from low resolution electromagnetic tomography (LORETA), the source localization method introduced by Pascual-Marqui et al. (1994).
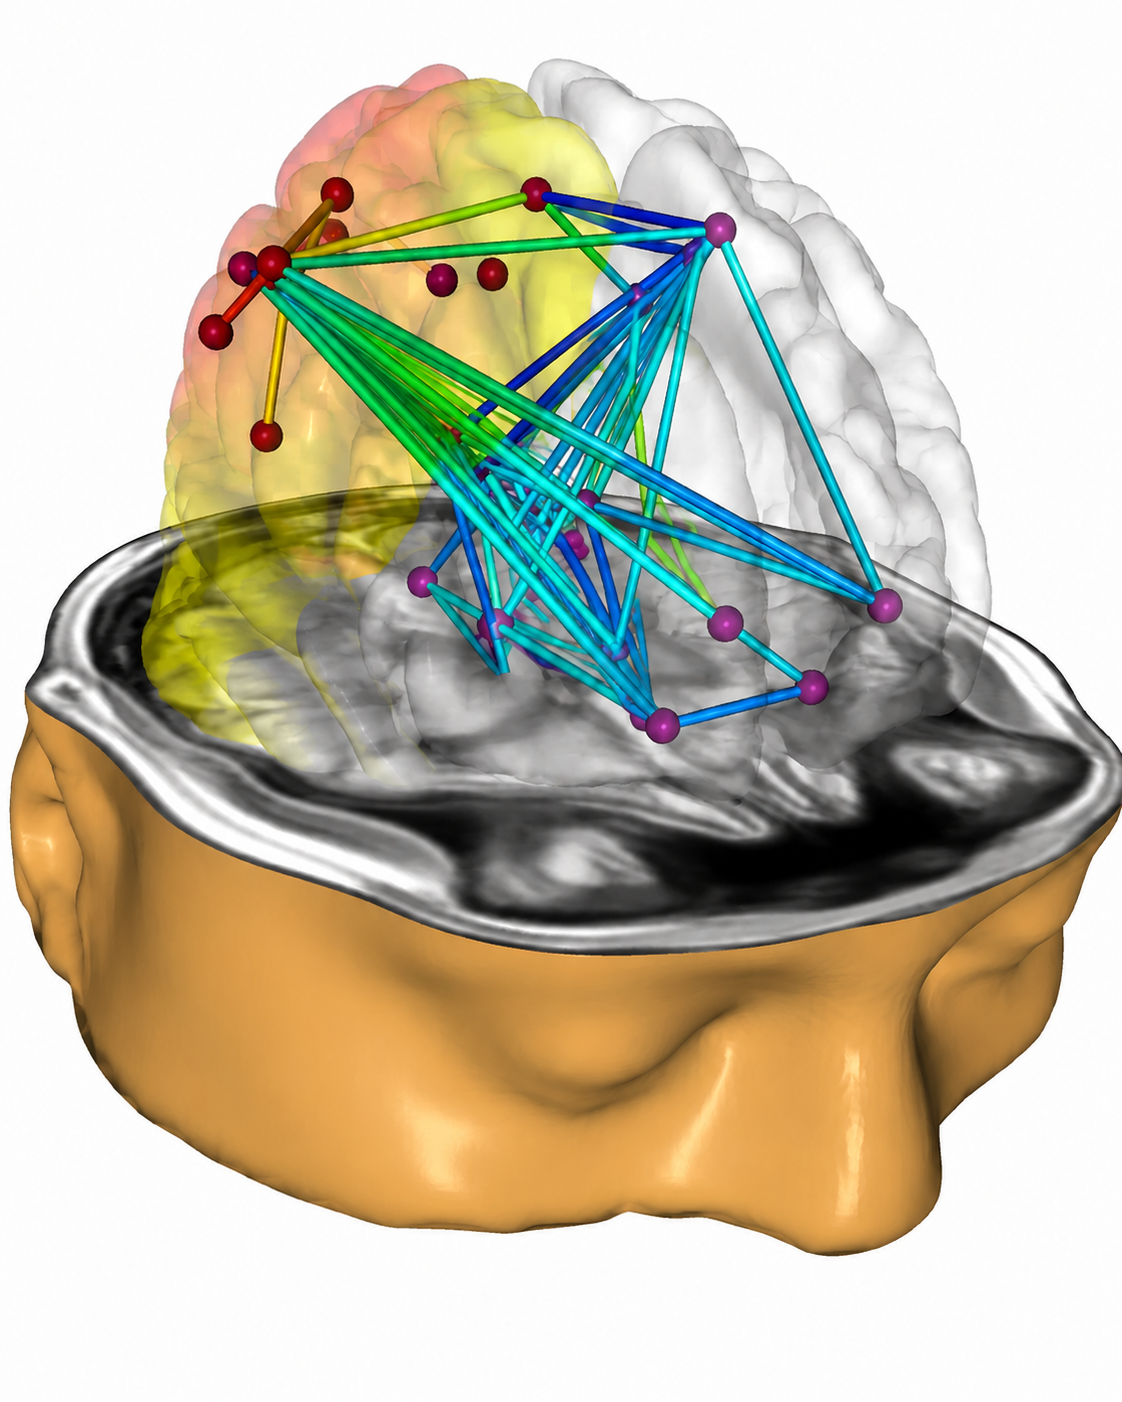
These advances have built a large community of clinicians using z-score neurofeedback. Applied Neuroscience maintains a bibliography of more than 50 publications on the method (https://www.appliedneuroscience.com/PDFs/Z_Score_NFB_Publications.pdf). Read that list as a measure of clinical uptake rather than of efficacy: it is vendor-maintained, mixes peer-reviewed articles with book chapters, newsletter pieces, a dissertation, and single-case reports, and contains no randomized controlled trials. For biofeedback practitioners, this growing evidence base means that z-score methods offer an option with growing support when client-specific EEG findings point to network-level dysfunction.
John S. Anderson provides an example of z-score training. Video © J. S. Anderson.
Research may also reveal EEG patterns of significance at particular locations and frequencies associated with a given disorder or symptom pattern. These findings become especially relevant when a research-based protocol proves ineffective, because the practitioner can then develop a client-specific protocol guided by the intersection of symptoms, the client's own EEG findings, and what the literature has identified about those EEG patterns.
The practitioner's guiding question is: "For my client's presenting complaints, is there a research-based protocol, or a set of research-based findings, that is relevant and corresponds to the client's EEG findings from the initial assessment?" The correspondence between symptom complaints, research findings, knowledge of brain-behavior relationships, and EEG assessment findings directs the practitioner to electrode placement locations, the frequency or parameter to train, and the direction of training.
If clinical reasoning suggests departing from research-based findings, the practitioner should be prepared to account for that decision. For instance, a client with ADHD may have shown poor benefit from theta/beta training but demonstrates abnormalities in the attention network that could account for their symptoms. In that case, an alternative method such as swLORETA z-score training to normalize the relevant network becomes a reasonable path to pursue. When a research-based protocol fails, the practitioner can draw on neuroscience and EEG research, interpreted in the context of the client's unique condition, to select an alternative approach.
Four types of research findings inform protocol selection: brain-behavior relationships and functional neuroanatomy, EEG correlates of clinical conditions, brain network anomalies, and neurofeedback efficacy studies. The practitioner seeks the best match between the client's presenting complaints, research-based protocols, and the client's EEG assessment findings. When research-based protocols prove ineffective, practitioners can draw on neuroscience knowledge and client-specific EEG data to develop individualized alternative protocols.
Environmental Context
The client's world outside the office, including relationships, living situation, and daily demands, can help or hinder neurofeedback training. Environmental factors matter less for choosing a protocol than for deciding how and when to deliver it. A stable family can be a major strength, while an unstable one may suggest waiting until circumstances are more supportive. There is another way to look at this, however. John Anderson's six years of experience in an inner-city, school-based neurofeedback program suggest that training itself can build a client's resilience and help them cope with the effects of difficult social, emotional, and family circumstances, rather than waiting for those circumstances to change.

Context cuts both ways. While excessive job demands may signal a poor time to begin training, the everyday demands of school or work can also be an advantage: they provide real-world situations in which clients can practice skills learned during neurofeedback and develop self-awareness about changes. The support of family and friends may assist both in the training office and at home, where remote training often depends on a family member's help. Whereas having a job is normally considered a strength, periods of excessive job demand may also be times to wait before starting neurofeedback.
Resources
Protocol selection is inevitably shaped by the tools at hand. Equipment resources range from single-channel to 19-channel systems, with software capabilities spanning amplitude and coherence training to the training of individual Brodmann areas or brain networks using z-score methods. Additional practical considerations include material resources for remote training, staff availability for scheduling multiple weekly sessions, and family resources for children who need transportation and support to attend appointments.
Client psychological resources are equally important. Internal resources such as motivation, self-awareness, communication ability, and cognitive capacity all influence readiness for neurofeedback. Training is most effective when the client is interested, can demonstrate some self-awareness, communicates at an age-appropriate level, and has stable physical and mental health.
When a client has fewer psychological or physical resources than average, preliminary steps can bridge the gap. These might include motivational interviewing to build readiness for change, peripheral biofeedback to enhance self-awareness, matching verbal information to the client's ability level, and scheduling sessions when health is most stable. In general, however, these accommodations affect how a protocol is delivered more than which protocol is selected.
Practitioner Expertise
Given the client's condition and the available evidence, the practitioner must honestly assess whether their training, skills, experience, and equipment allow them to provide effective training. One key factor is the neurofeedback model to which they subscribe. Because different models have different applications, a practitioner trained in multiple models has the broadest armamentarium from which to draw when addressing a client's goals.

Most practitioners will have expertise in an evidence-based model grounded in scientific investigations of neurofeedback efficacy and effectiveness, as described in Evidence-Based Practice in Biofeedback and Neurofeedback (4th ed.; Khazan et al., 2023). Beyond this foundation, models based on clinical studies and the neuroscience of brain-behavior relationships may be essential when research does not provide strong support for a specific protocol. In those situations, the practitioner must draw on clinically-based models and neuroscience knowledge to guide the training plan.

Ethical principles are central here. Practitioners should provide neurofeedback only for conditions for which they have adequate training, or they should seek supervision. Ideally, the practitioner will have sound understanding and experience with the client's clinical condition, skill with neurofeedback methods for that condition, and knowledge of how it relates to brain and psychophysiological findings.

Client Values and Preferences
After weighing all the preceding factors, the practitioner presents the client with a formulation: a description of the problem, a provisional model of its cause, and suggested training options. The options, with their likely costs and benefits, are reviewed so the client can make an informed decision about whether to pursue neurofeedback and, if so, which method to use. This process respects the ethical principle of autonomy, fulfills the requirement for informed consent, and acknowledges the client's own values and preferences.

Protocol selection requires weighing six interrelated factors: the client's condition and goals (assessed at biological, psychological, and behavioral levels), research findings, environmental context, available resources (equipment, staff, and client readiness), practitioner expertise, and client values and preferences. Ethical principles of autonomy and informed consent are central throughout. Consideration of age-appropriate EEG activity, social and academic performance, and the context in which these occur is important. A holistic developmental biopsychosocial description of the client, combined with neuroscience knowledge, ultimately guides electrode placement and EEG variable selection.
Decision-Making and Ongoing Problem-Solving
This section covers how the factors just reviewed translate into an evidence-based, collaborative decision-making process, from initial protocol selection through ongoing monitoring and adjustment. The approach is biopsychosocial: it combines biological, psychological, and behavioral evidence, along with the social context in which these are seen, together with the client's active participation to select protocols that are most likely to help and least likely to cause harm.
Together with the choice of a training protocol, the practitioner and client should agree on explicit, measurable goals at one or more levels of analysis. At a biological level, changes in EEG variables are one type of goal. At a psychological level, neurofeedback may aim to improve emotional regulation or cognitive function. At the level of observable behavior, goals may target specific actions in context, such as academic performance at school or attentional focus in a competitive sport. Goals are typically measured and quantified using the same methods employed during the initial assessment.
Once a protocol is underway, the neurofeedback provider should conduct ongoing assessment of EEG, psychological, and behavioral variables so that progress can be reviewed with the client. If improvement toward the client's goals is not seen within a reasonable time, the provider should re-assess and generate new training options. Adjustments or alternative protocols should also be considered if unwanted side effects occur. Neurofeedback concludes when goals have been achieved or when no further progress is evident.
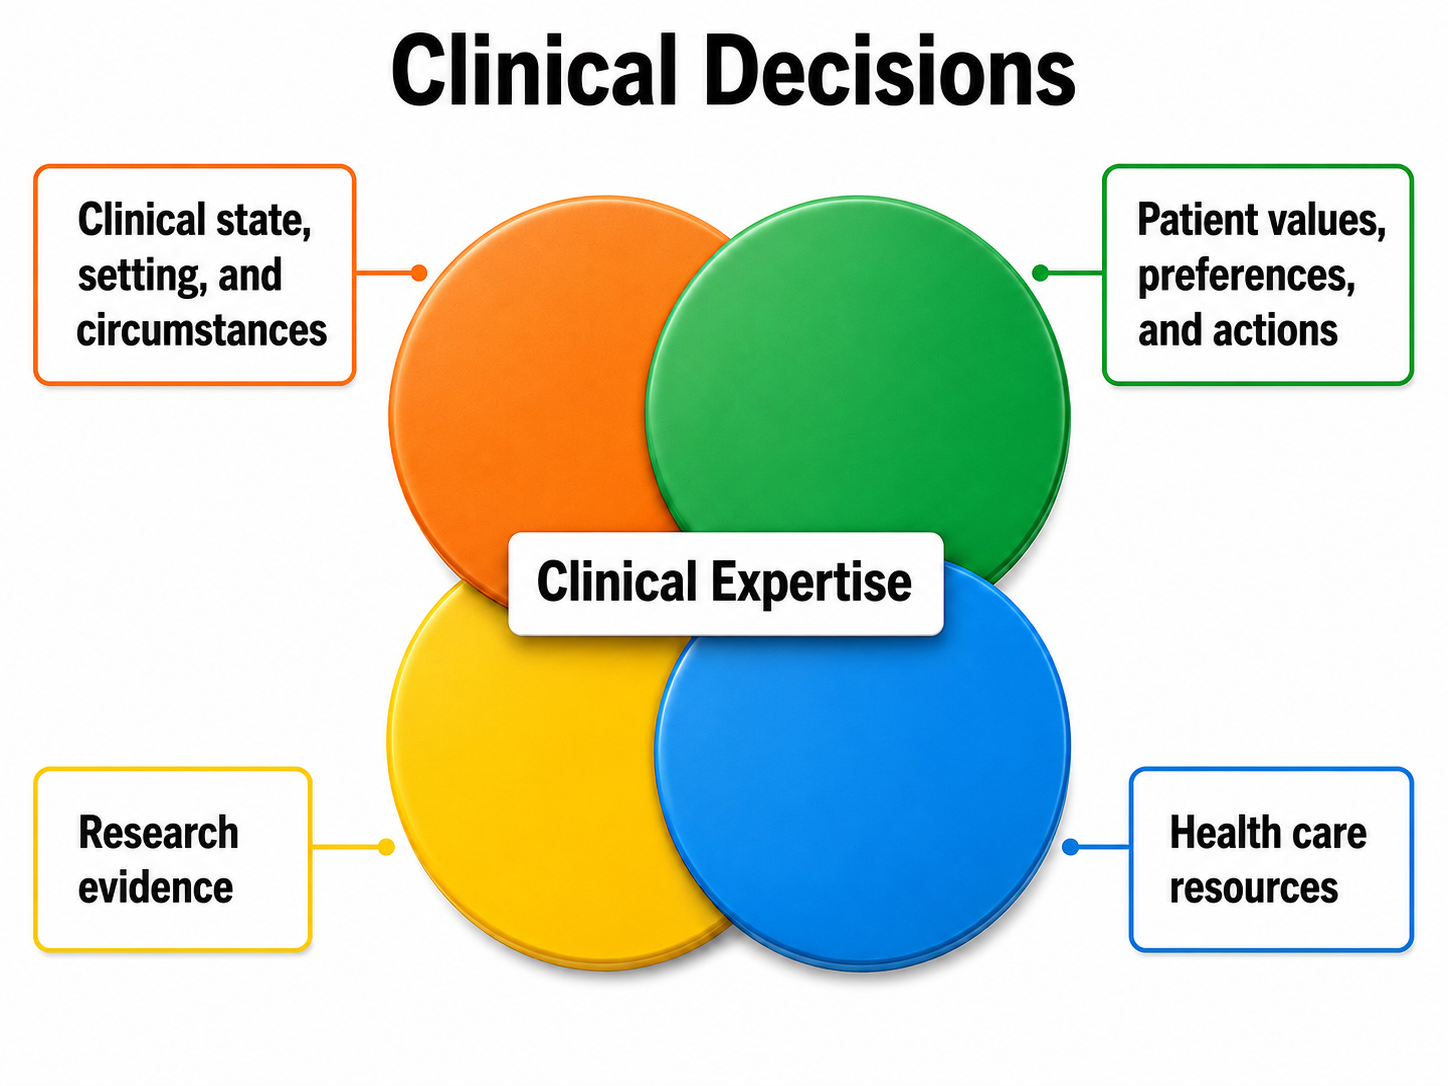
Flowchart
The factors discussed above can be organized into a practical decision-making flowchart. This flowchart is intentionally simplified; practitioners should be prepared to depart from it when there are valid clinical reasons, and they should always be able to account for their reasoning when they do so.
For any individual case, the relative weight of each factor will vary, making one component more prominent in choosing a training regimen. This variability is a feature, not a flaw: it reflects the reality that each client is unique. The flowchart also gives the practitioner recourse for problem-solving when an initially chosen training plan fails to provide sufficient benefit.
Below is a simplified flowchart that depicts the preceding discussion.
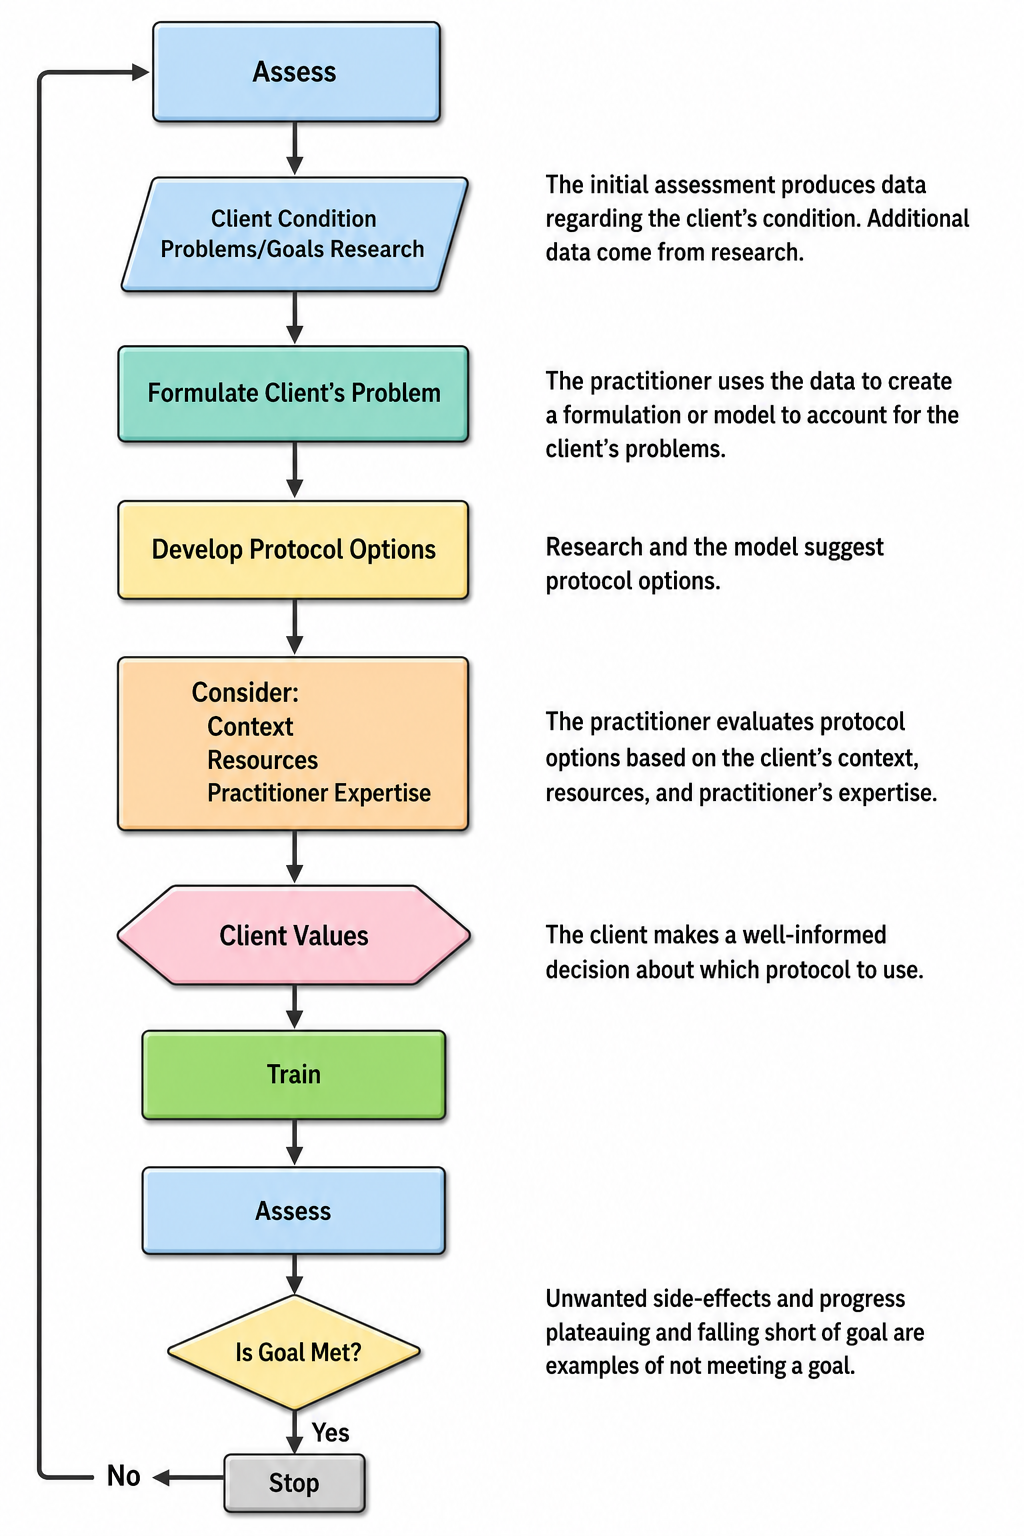
Underlying the flowchart's Formulate Client's Problem and Develop Protocol Options steps are four key questions: (1) What is the client's psychological or behavioral problem? (2) What does the EEG reveal about location and EEG parameters? (3) What do other tests show? (4) What research evidence supports the efficacy of a neurofeedback protocol for the issues identified by questions 1 through 3?
In essence, the practitioner is looking for the best match between problems and protocols to address them. The strongest starting point is usually a protocol with supportive research evidence, introduced in a trial-and-error manner to test the hypothesis that it will be effective. If the hypothesis is not confirmed, the practitioner selects an alternative research-based protocol if one is available. Failing that, the practitioner draws on their understanding of neuroscience, brain-behavior relationships, and EEG research to make informed decisions about electrode location, training frequency, frequency parameter, and the direction of training.
Decision-making in neurofeedback follows an evidence-based biopsychosocial approach. Goals should be explicit and measurable at biological, psychological, and behavioral levels. Ongoing assessment monitors protocol effectiveness, and adjustments are made when progress stalls or side effects emerge. The decision-making flowchart guides the process through four questions: identify the client's problem, assess the EEG, consider other test findings, and match these with research-supported protocols. When initial protocols fail, practitioners draw on neuroscience knowledge and client-specific data to develop alternative approaches.
Neurofeedback as Training: A Learning Model
Before we walk through the steps from assessment to training, it is worth being clear about what neurofeedback actually is, because the words we use shape what clients expect, and expectancy can influence outcome in significant ways. Medical treatment is something done to a person. A medication, a surgery, or a stimulation procedure acts on a mostly passive recipient, and the effect depends on the dose. Neurofeedback is different.
The equipment doesn't put anything into the brain. It measures the client's own EEG and gives that information back quickly enough for the brain to learn from it. Whatever changes happen are produced by the client's own nervous system, through practice. That is why neurofeedback is best understood as training, and the client as a learner.
The Research Basis for a Training Model
The traditional explanation for EEG changes produced by neurofeedback is operant conditioning: a brain state that is promptly followed by a reward becomes more likely to happen again (Sherlin et al., 2011). Sherlin and colleagues argued that clinical practice, research, and equipment design should all follow basic learning principles, and Kerson et al. (2026) recently revisited and updated that framework. Strehl (2014) went a step further, recommending that neurofeedback be delivered within a behavior-therapy framework that bridges the brain level of analysis to the real-life behavior level, where the practitioner guides the learning and the equipment is simply a tool. Consider that once behavior change in the relevant social situations has developed and is being reinforced by natural contingencies, brain changes such as those at the EEG level of analysis may be more likely to be maintained themselves. As you will see later in this section, however, not everyone agrees that operant conditioning is the whole story.
The outcome data look like what you would expect from a learned skill. In a meta-analysis of ten randomized controlled trials in children with ADHD, Van Doren et al. (2019) found that parent-rated inattention improved with a medium effect at the end of neurofeedback training (SMD = 0.64) and a large effect at follow-up 2 to 12 months later (SMD = 0.80). The small gains in non-active control groups were no longer significant at follow-up. Active comparison conditions, mainly methylphenidate, produced large effects that held steady but did not grow after the intervention ended. Arns et al. (2020) likewise reported that the medium effects of standard protocols lasted 6 to 12 months.
That pattern makes sense. A medication's effects usually fade once it is stopped, while a skill that has been learned stays with you and can keep getting stronger with everyday use. These findings rest mostly on parent ratings, which are not blind to group assignment, so they support the learning model without proving it.
The training model changes everyone's role. The client is a trainee who practices a skill, notices what helps, and reports what changes between sessions. The practitioner is a trainer and coach who designs the training plan, sets reward criteria, watches for artifacts, and makes sense of the progress. Family members, teachers, and employers can become practice partners who help the new skill carry over into daily life. That is, they can also be thought of as trainees whom the clinician teaches to change their behavior in ways that support the identified client's behavior change.
So how do we measure progress? By learning (Is the client gaining control of the trained EEG parameter?) and by transfer (Is that control changing life outside the office?), not by the number of sessions delivered. These reflect processes of learning that have been experimentally investigated for decades, such as response acquisition and generalization, whether response generalization to other similar responses, situational generalization of the response to other stimulus situations, or temporal generalization that preserves the response over time after the training has ended.
Two Ways of Framing Neurofeedback
| Treatment framing | Training framing |
|---|---|
| The client is a patient who receives an intervention. | The client is a learner who practices a skill. |
| The practitioner administers a procedure. | The practitioner designs the plan, coaches, and adjusts the training. |
| Change is produced by the device. | Change is produced by the client's own nervous system through practice. |
| Sessions are doses. | Sessions are practice opportunities, spaced to allow consolidation. |
| Progress means symptom reduction alone. | Progress means learning the trained parameter, transferring it to daily life, and reaching goals. |
| It ends when the course is delivered. | It ends when skills are mastered and maintained without feedback. |
| "It didn't work." | "I haven't learned it yet. What should we change in the training?" |
Stages of Learning Self-Regulation
Neurofeedback learning seems to follow the same course as any other skill. Strehl (2014) mapped it onto the three phases described by Fitts and Posner (1967). In the cognitive phase, the client tries out different mental approaches, makes lots of errors, and finds the whole thing effortful. In the associative phase, the client starts to link particular internal states with reward, and performance becomes more consistent.
In the autonomous phase, the skill takes little conscious effort and can be produced without the feedback display. Anyone who has learned to ride a bicycle or play an instrument will recognize the sequence.
Davelaar (2018) proposed a complementary model with three stages. In the first, exploration, the trainee tries different mental strategies, and frontal-striatal circuits are strengthened whenever a strategy produces reward. In the second, consolidation, a strategy reliably produces reward, and changes along striatal-thalamic pathways may begin to show up in the resting EEG. In the third stage, which not every learner reaches, the bodily and subjective feel of the target state becomes more noticeable.
Because that feeling has been paired with reward, this interoceptive awareness becomes rewarding in its own right and helps the client find and hold the state without equipment. This is where training starts to become part of everyday life.
What does this mean in practice? Early sessions can be frustrating, so let clients know to expect a learning curve. Telling a client exactly what mental strategy to use is usually unnecessary and may even slow things down. Strategies tend to emerge on their own, and in some studies the participants who reported no particular strategy learned best (Strehl, 2014).
A better coaching stance is curiosity. Ask clients what they notice when the rewards come more easily, and help them put words to that state so they can find it again outside the session.
Learning Principles That Shape Every Session
Feedback must be immediate. Conditioning weakens when the reward is delayed by more than a fraction of a second. Sherlin et al. (2011) recommended keeping total feedback latency below about 250 to 350 ms, which has direct implications for how you set filters and software.
Reward must be contingent and clean. Rewarding eye blinks, muscle tension, or movement teaches the wrong behavior, so real-time artifact detection and close observation by the trainer are essential (Sherlin et al., 2011; Strehl, 2014).
Shape performance in planned steps. Shaping reinforces successive approximations to the target. Both Sherlin et al. (2011) and Strehl (2014) caution against relying on automatic thresholds that hold the reward rate constant no matter how the client is doing, because those thresholds can reward a session that is worse than the one before. Decide on the end goal and the steps along the way, and adjust thresholds on purpose.
Keep the brain-reward link clear. The feedback display should make the connection between brain state and reward obvious. Sherlin et al. (2011) warn that complex games and continuous videos can compete with that link, and that points or prizes should be tied to actual EEG change rather than to attendance. Others see it differently. Game-based displays can make training more engaging, and engagement matters, because a dull, unchanging task quickly loses a client's interest over a long course of training (Yang et al., 2026).
In Yang and colleagues' study, 50 young people, half of them with ADHD, trained with an EEG-controlled skiing game whose difficulty adjusted to each player's attention level, and EEG attention scores in the ADHD group rose by 21.5%. The authors are careful to note that with only two sessions and no sham-feedback control, these are short-term effects rather than proof of learning. Practitioners with long experience of game-based feedback, John Anderson among them, find that entertaining displays reduce resistance and encourage the effortless, non-cognitive learning described earlier as interoceptive awareness. In another brain-computer interface study, participants who heard sounds linked to their changing brain state reported less frustration and more motivation than those who saw only a bar (Sollfrank et al., 2016).
Either way, the key is the same. When thresholds and feedback are set correctly, the client must achieve the target state change for the feedback to proceed. A video that brightens and dims, with sound that rises and falls along with it, rewards change continuously and may be even more reinforcing than discrete, event-related feedback.
A school-based example. New Visions School in Minneapolis, a public charter school for grades 1 through 8 operated with A Chance to Grow, made neurofeedback part of the regular school day in the early 1990s. The program reported that it was the first public school in the United States to do so. All training used game-based feedback: a "Mazes" game similar to Pac-Man, and "Islands" or "Highways" games in which three boxes changed size with EEG and muscle (EMG) amplitude against a changing visual background. Protocols generally followed EEG Spectrum guidelines, rewarding 12 to 20 Hz activity while inhibiting 4 to 7 Hz activity and muscle tension, usually in two half-hour sessions a week.
Over four school years (1994-95 through 1997-98), the program grew from 42 to 75 students a year. In each year, between 82% and 100% of the students retested on the TOVA after at least 20 sessions improved on at least one scale, and in 1997-98, 84% of the 32 students retested on the Conners' CPT improved on at least one variability scale. Variability, the steadiness of attention over time, was the scale that improved most often. Staff also noticed that students who completed 40 or more sessions generally gained more than those who completed 20 to 30 (Anderson, 1995, 1996, 1997, 1998).
These were internal program evaluations without control groups. Many of the students were more severely impaired than typical research participants, and some could not take the tests at all. So the reports do not prove that the training worked. What they do show is that children with significant attention and behavior problems could stay engaged with game-based feedback, twice a week, often for years, as part of their school day.
Space the practice. Spaced practice generally works better than massed practice, and with sessions of 20 to 60 minutes, more than one session a day is impractical for most clients anyway (Strehl, 2014). Watch for signs of overtraining, such as the occasional overactivation reported by Client A. They suggest that a protocol has gone far enough.
Plan for transfer from the start. Feedback after every trial speeds early learning, but practice with reduced feedback produces better long-term retention. Transfer trials, in which the client tries to produce the target state without the display and learns only whether the attempt succeeded, help move the skill into daily life (Sherlin et al., 2011; Strehl, 2014).
Expect individual differences. Clients learn at different rates, and some do not learn to regulate the trained parameter at all (Alkoby et al., 2018). Systematic reviews point to attention, motivation, and mood as psychological factors that influence learning, alongside neurophysiological measures taken before training (Cohen Kadosh & Staunton, 2019; Weber et al., 2020). Tracking learning session by session lets you tell apart a client who is not learning, who needs a change in feedback, instructions, or protocol, from one who is learning but not yet seeing benefit in daily life.
An Alternative Perspective: Othmer's Endogenous Neuromodulation Model
Not every experienced practitioner accepts operant conditioning as the full explanation of how neurofeedback works. Siegfried Othmer, a physicist who with Susan Othmer has developed and taught clinical neurofeedback for several decades and who developed infra-low frequency (ILF) training, has written extensively on an alternative view. Much of his recent thinking appears in essays, clinical training materials, and the EEG Institute's online publications rather than in peer-reviewed journals, so it is presented here as an alternative perspective to weigh against the learning model, not as established findings.
The brain, not the trainer, does the regulating. Othmer describes the brain as continually comparing its own activity with what is happening in the world. When it is shown a continuous display of its own activity, the brain, as the author of that signal, recognizes itself in it and uses the information to move toward better regulation. Othmer calls this process endogenous neuromodulation (Othmer, 2007, 2024).
On this view the client does not need to understand the display or deliberately control it. In Othmer's words, self-regulation "always was and will always remain largely out of our abiding voluntary control" (Othmer, 2007).
Operant conditioning is not the operative mechanism. Othmer argues that strict adherence to the Skinnerian model made early protocols inefficient. He also argues that the rapid state changes clinicians observe, sometimes within the first 6 to 10 minutes of a session, are hard to explain as conditioning, which takes time to build (Othmer, 2024). In ILF training the target signal changes too slowly for amplitude thresholds to define discrete rewards, and Othmer and Othmer (2016) state that operant conditioning therefore "had to be abandoned formally as the operative model." Feedback is continuous rather than reward-based, and rewards and inhibits are treated as "a provocation or a challenge rather than as an explicit instruction."
Training is optimized by the client's state, not prescribed in advance. Othmer and Othmer (2016) describe the method as "non-prescriptive." Training usually begins at bipolar right-hemisphere or cross-hemisphere placements (T4-P4 for arousal regulation, T3-T4 for brain instability), and other sites are added as needed. Rather than working from qEEG targets, the trainer adjusts the target frequency, often well below 0.1 Hz, according to the client's moment-to-moment and session-to-session reports, searching for an optimal response frequency at which the client is "optimally calm, alert, and euthymic." qEEG-guided training is reserved for later, more specific goals once basic regulation is stable (Othmer, 2010).
The relationship amplifies the effect. Othmer regards co-regulation between client and practitioner, much like that between mother and infant, as one of several "compounding factors, not confounding ones": influences that multiply the effect of the feedback rather than explain it away (Othmer, 2024).
How does this view fit with the training model presented in this unit? The two agree on the essentials. The client's own nervous system produces the change, nothing is done to a passive recipient, and the practitioner's job is to create conditions in which the brain can reorganize itself. They differ on mechanism, and therefore on technique. The learning-theory model emphasizes contingent reinforcement, shaping with deliberately set thresholds, and gradual skill acquisition, whereas Othmer's model emphasizes continuous information, frequency optimization guided by client report, and state change that can begin within a single session.
The evidence bases differ as well. ILF training has been described in peer-reviewed case reports and clinical studies (e.g., Legarda et al., 2011; Othmer et al., 2013) and in a large uncontrolled clinical data set from 2006 to 2014, in which 5,746 clients' impulsivity scores on the QIKtest, a TOVA-like continuous performance test, were compared before and after nominally 20 ILF sessions (Othmer & Othmer, 2016). It has not yet been tested in large randomized controlled trials like those for standard ADHD protocols.
The Othmers' earlier clinical network used a different, amplitude-based approach. In a multi-center study of 1,089 clients at 32 EEG Spectrum-affiliated clinics, training rewarded 15-18 Hz at C3 or 12-15 Hz at C4 while inhibiting 4-7 Hz and 22-30 Hz activity, with displays in which EEG amplitude controlled the brightness, size, or speed of objects on the screen. After 20 or more sessions, TOVA scores showed significant improvements in attention, impulse control, and response variability (Kaiser & Othmer, 2000). Practitioners who adopt Othmer's approach should explain it to clients as one option among several, monitor outcomes carefully, and be prepared to account for their choice, as they would for any protocol.
Here is an interesting wrinkle. Most feedback displays that clients actually see, whether the practitioner is thinking in terms of operant conditioning or endogenous neuromodulation, include some kind of continuous, proportional feedback.
The simple bar graph, long a common way to show a client's training frequency information, is a good example. The bar moves up and down with the client's EEG activity in real time, in a format that is easy to understand. An example is shown below.
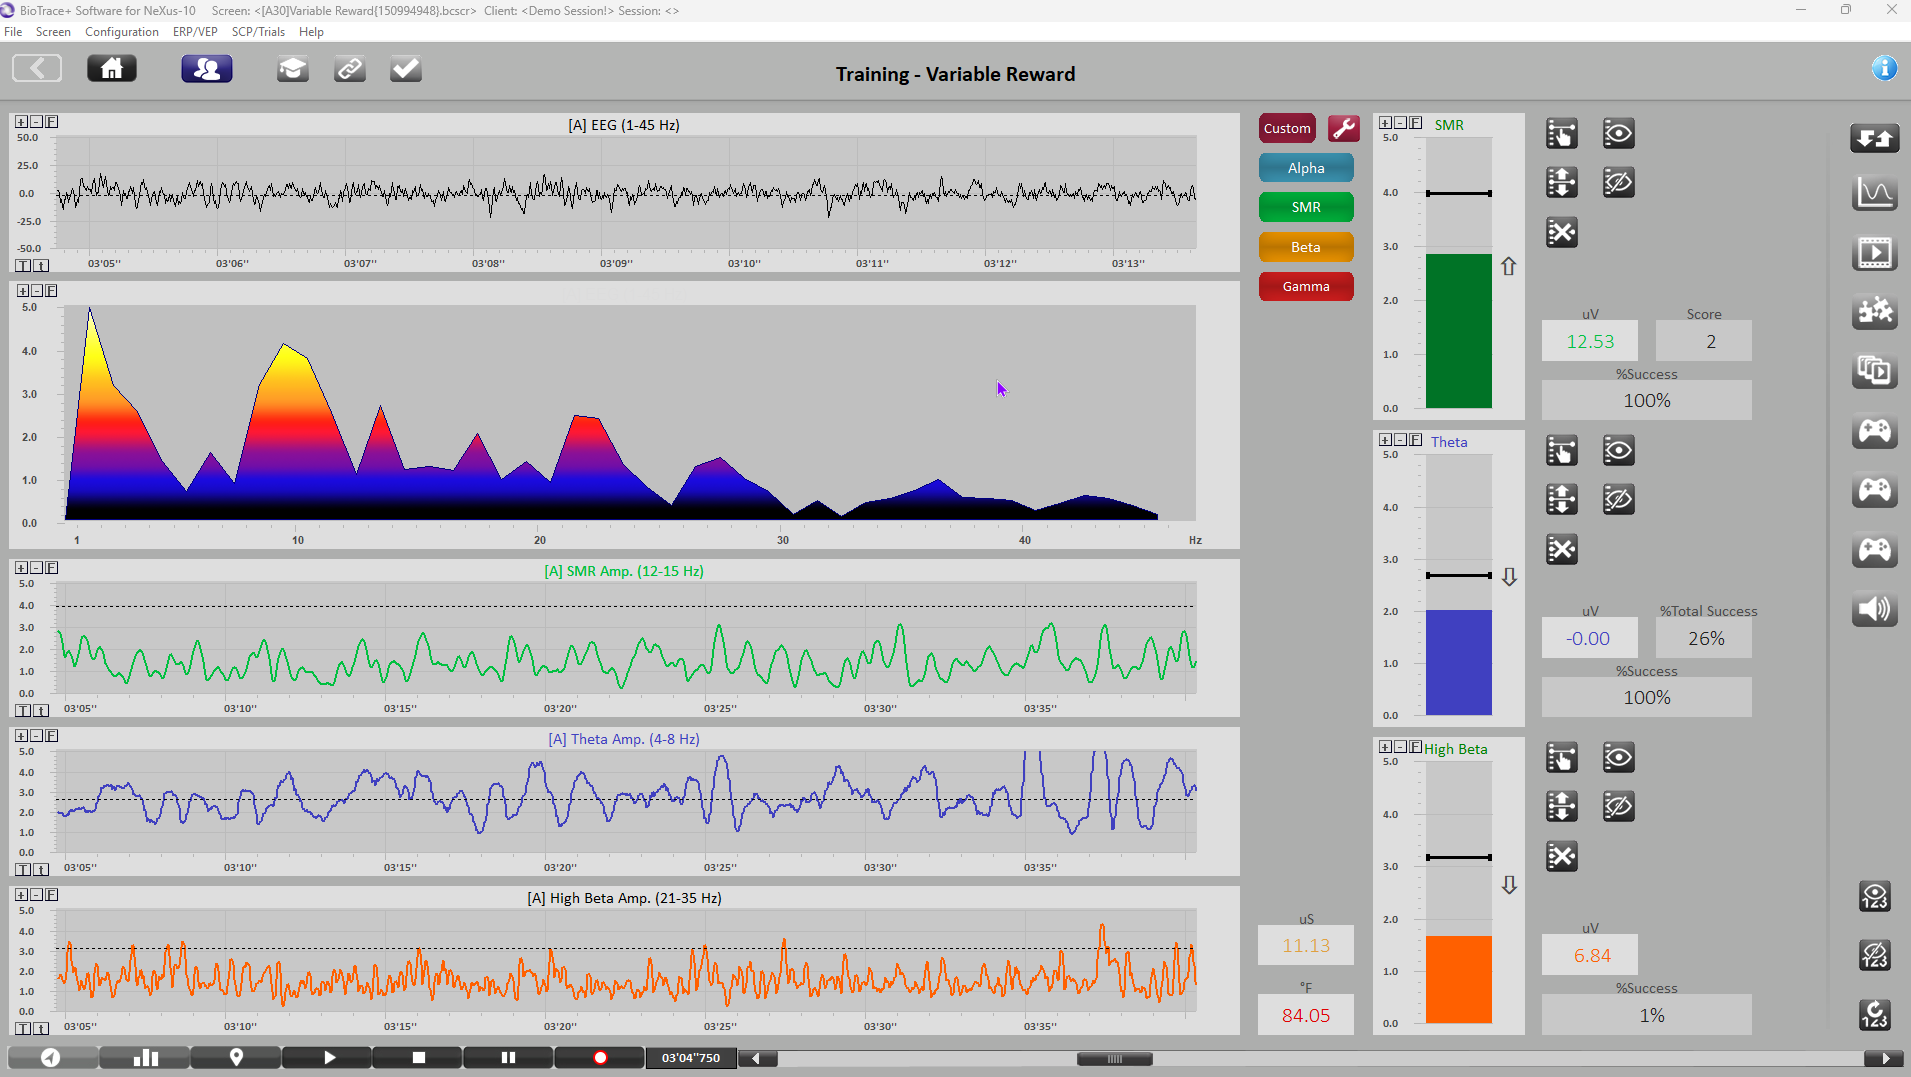
This is a screen from the NeXus/BioTrace+ system. It is a single-channel demonstration recording showing a variety of information as line graphs, bar graphs, and spectral displays. This is not typically what the client sees, though they may see it during the setup phase of the process. Below is a more typical client screen showing a visual display that brightens and dims as the client moves toward or away from set goals. Note that bar graph displays are also provided.
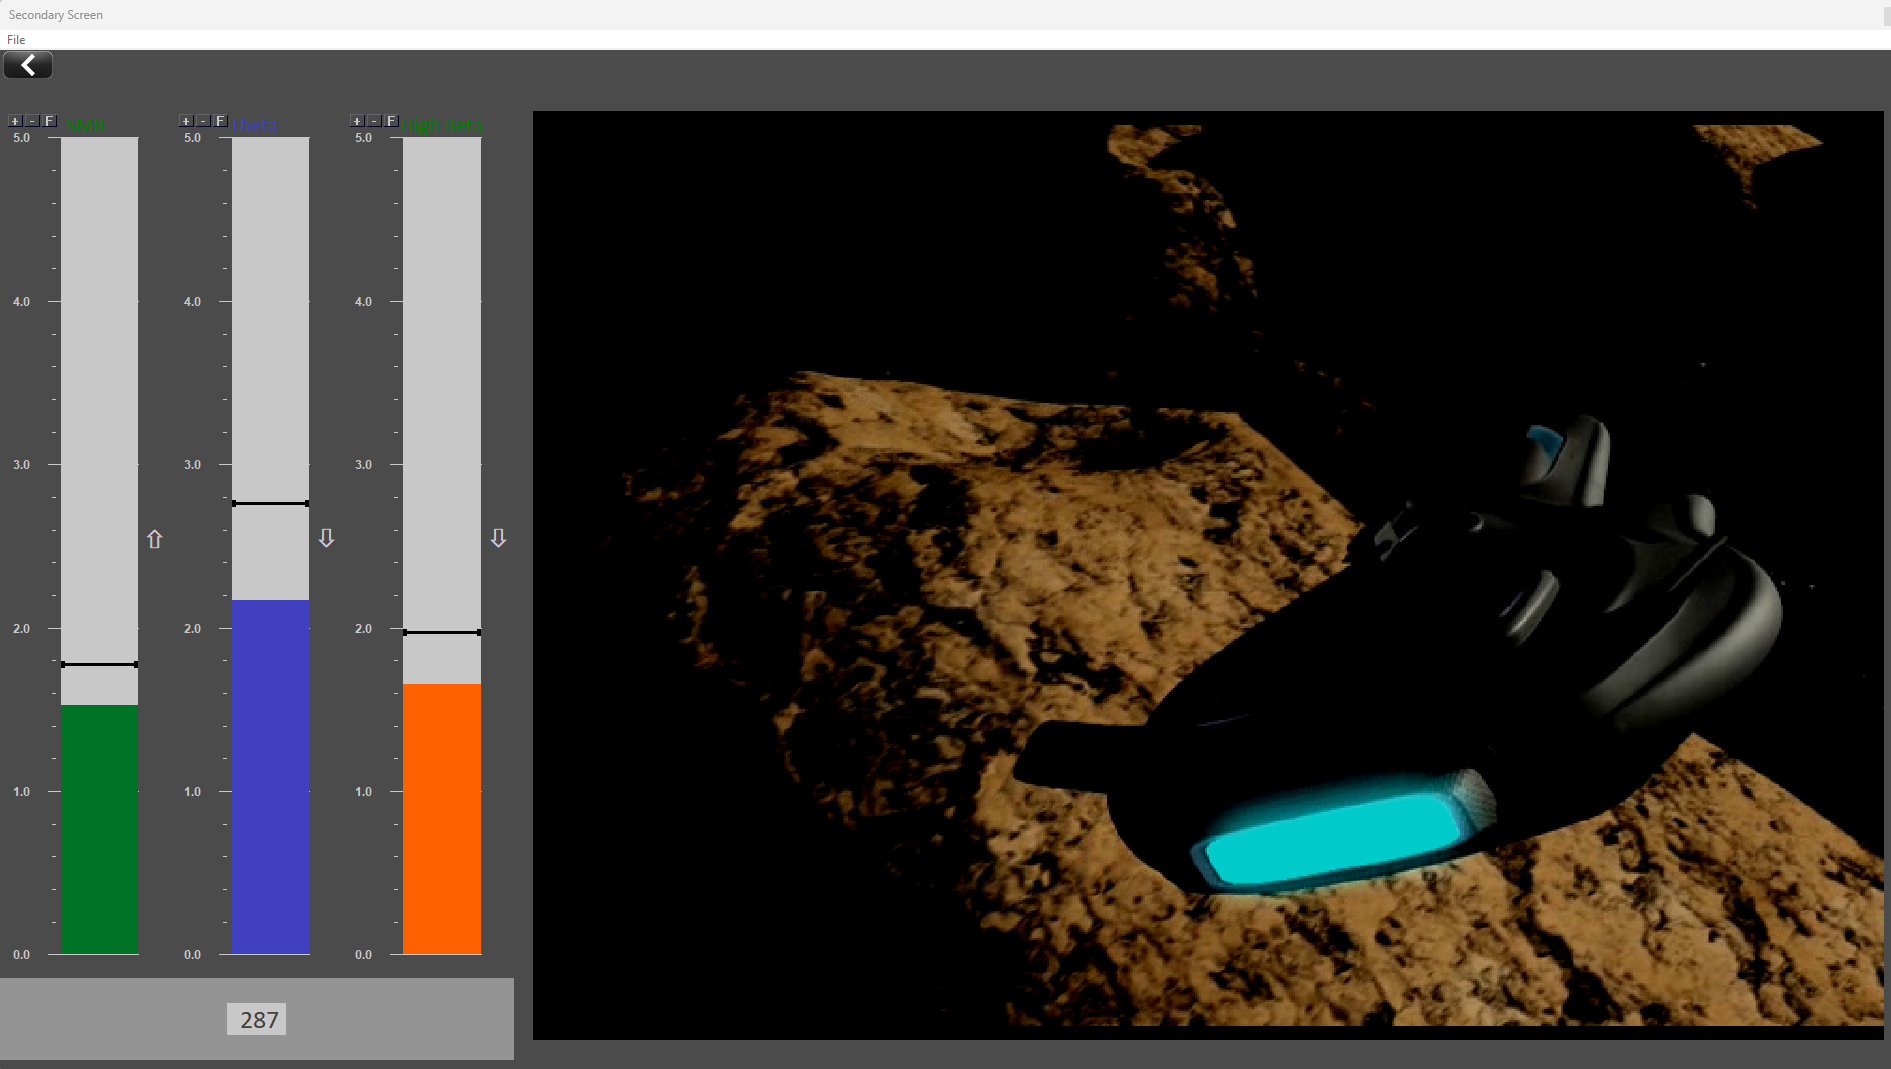
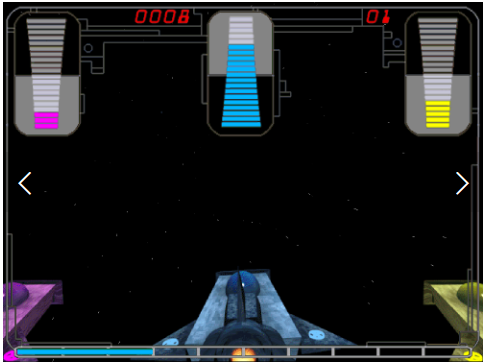
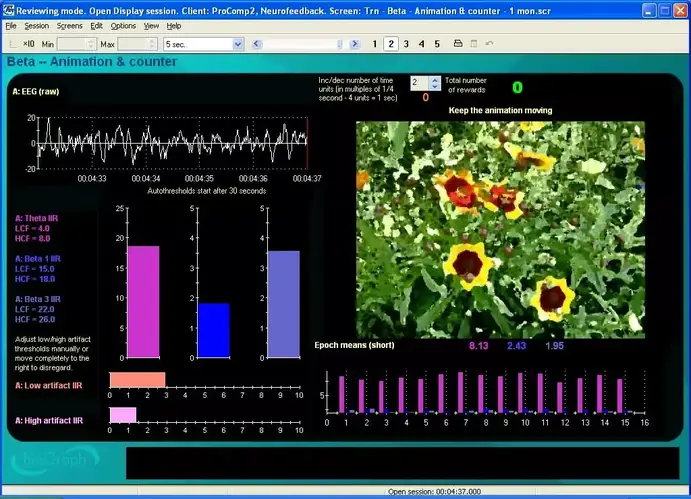
These examples show that some sort of continuously variable informational display, such as a bar graph, is included in many neurofeedback software platforms. This suggests that the outcomes of studies framed as strict operant conditioning may have been affected by the presence of such feedback, unwittingly providing the clients with an endogenous neuromodulation feedback experience. Even the simple use of rewards that vary with performance, as is common in many neurofeedback training game systems, involves continuously variable components. Zukor Air, which is used with multiple neurofeedback and biofeedback systems, is one example, shown below.
Continuous and Discrete Feedback: What the Research Shows
Can continuous, proportional feedback drive learning all by itself? A small animal study suggests it can. Fokina et al. (2010) trained two cats using white noise that grew quieter as the frontal beta/theta power ratio rose. During feedback sessions, beta power increased, theta power decreased, and the ratio rose significantly. None of this happened in control sessions, where the sound level was replayed from an earlier session and had nothing to do with the cat's ongoing EEG.
Firing of presumed dopamine neurons in the ventral tegmental area also rose during feedback sessions, which suggests the changing signal itself acted as a reward. With only two animals, the study is far from conclusive, but it shows that a continuous signal can shape the EEG without instructions, understanding, or a separate reward event. Both models in this unit can claim it. A learning theorist would call the quieter noise continuous negative reinforcement, while Othmer would see the brain responding to its own signal.
Learning theorists argue that discrete reward events still add something. One reason is post-reinforcement synchronization (PRS), a brief burst of alpha-like EEG activity that follows a reward. Marczynski et al. (1981) measured PRS over the visual and association cortex of 25 cats as they learned to press a lever for milk. The cats with the largest PRS learned fastest (r = 0.77), while the slow learners spent far longer repeating behaviors that no longer paid off. The researchers also noticed that PRS was much more conspicuous when a cat had earned its reward than when it was given the same amount of milk for free.
In other words, the brain responds most strongly to rewards that follow its own performance. Hallschmid et al. (2002) later recorded similar synchronization after reward in humans. A discrete reward event creates a moment in which PRS can occur, which is one reason Strehl (2014) concluded that the best arrangement is "probably the combination of correct feedback and reinforcement": continuous information about the trained activity, together with positive reinforcement when the target is reached. Keep in mind that these are correlations in cats, not proof that PRS causes learning.
The type of feedback matters too, and one of the oldest direct comparisons is still one of the most interesting. Travis et al. (1974) trained 56 adults to increase occipital alpha. Some heard a binary tone that came on only when alpha passed a threshold. Others heard a proportional tone whose pitch rose smoothly with alpha amplitude. Both were compared with random-feedback and no-feedback control groups.
With eyes closed, only the proportional groups produced significantly more alpha than the controls, and binary feedback did no better than random or no feedback. With eyes open, the result reversed, and binary feedback produced larger increases than proportional feedback. The authors pointed out that the proportional signal carries more information, telling the trainee about every level in between, while the binary signal says only whether the target was reached. They suggested that eyes-open and eyes-closed alpha enhancement probably depend on different mechanisms.
Each condition was trained for only one day of ten 5-minute periods, so the binary groups might have caught up with more practice. The lesson is not that one kind of feedback is always better. The better choice may depend on the task and the state being trained.
Direct comparisons in humans are still few. Sollfrank et al. (2016) trained 30 newcomers to control a motor-imagery brain-computer interface over five sessions, using one of three displays: a conventional moving bar, an enriched visual "funnel" display, or the same funnel display with sounds that changed as control improved. In the first session, the group with the combined visual and auditory display performed significantly better than the bar group, and across all five sessions those participants reported more motivation and less frustration. Accuracy varied widely from person to person, which will be a familiar story to anyone who has trained clients.
So what should a practitioner do? Keep a clear continuous display, such as a bar graph, at the center of training, and add discrete, event-related rewards and sounds for engagement and motivation. No single arrangement has yet been shown to be clearly superior, and the right choice may depend on the client and on the state being trained.
Neurofeedback is training, not treatment. It draws on several learning approaches so that clients learn to regulate their own brain activity, with the practitioner serving as trainer and coach. Skill learning seems to move from an effortful, exploratory stage, through consolidation, to automatic, interoceptively guided self-regulation. Effective sessions provide immediate, contingent, artifact-free feedback, shape performance in planned steps, space practice, and build in transfer from the start.
Most feedback displays combine continuous, proportional information with discrete reward events. Continuous feedback can drive learning on its own (Fokina et al., 2010), earned rewards produce post-reinforcement synchronization that tracks learning ability (Marczynski et al., 1981), and the better form of feedback may depend on the task (Travis et al., 1974). No arrangement has yet been shown to be clearly superior. Follow-up data showing that gains persist or grow after training ends fit this learning model. An alternative perspective, Othmer's endogenous neuromodulation model, agrees that the client's brain does the work but attributes the change to the brain's engagement with its own continuous signal rather than to operant conditioning.
From Assessment to Training
This section walks through the full training arc, from the intake interview through protocol selection, training, and reassessment, followed by two client case examples. The process can be organized into nine steps. They are listed in order, but in real life they overlap. Assessment continues throughout training, and the plan changes as you learn how the client responds.
Step 1: Screen for functional causes. Before training begins, check for the red flags described earlier in this unit and make referrals when needed. Self-regulation training is most effective once medical contributors have been ruled out or addressed.
Step 2: Conduct the intake and orient the client to training. The process begins with the client intake interview, often facilitated by history and symptom forms completed beforehand. Once the client's presenting concerns are identified and discussed, the history of those concerns, including prior interventions and their degree of success or failure, shows how resistant the concerns have been to previous approaches. The client's reasons for seeking neurofeedback can also be explored, and this is often the ideal moment to explain the underlying concepts of biofeedback and neurofeedback training. Emphasizing that neurofeedback is training, not treatment, is particularly important at this stage of the developing relationship.
Establishing clear roles for both the client and the trainer is essential. Many clients expect neurofeedback to be passive, something done to them, like taking medication or receiving repetitive transcranial magnetic stimulation (rTMS). Because all biofeedback involves active training and education, this distinction can be difficult for some clients to accept. Comments like "it didn't work" or "that didn't do anything" reflect a disconnect between expectations and the reality of the training process, and this gap may need to be addressed throughout training. A useful comparison is learning a musical instrument or a sport: progress comes from regular practice with good coaching, early sessions may feel awkward, and the skill becomes easier and more automatic over time.
Step 3: Assess and establish baselines. Once the client understands the nature of the biofeedback training process, the clinician proceeds with appropriate testing. Foremost among these will be objective physiological evaluations such as autonomic nervous system reactivity, EEG behavioral characteristics and task responses, questionnaire measures, and possibly a continuous performance test or other computerized neurocognitive assessment. These measures serve two purposes: they guide protocol selection, and they provide the baseline against which learning and progress will later be judged.
Step 4: Formulate, set goals, and obtain agreement. All intake and testing information is evaluated, and a training plan is designed using the factors and flowchart described earlier. Goals are stated in measurable terms at the biological, psychological, and behavioral levels. The training plan is described to the client, and their agreement to participate is obtained.
This agreement is an ongoing component of the process; before each subsequent session, the client's responses to previous training are briefly evaluated, and the client is asked whether they wish to continue. Any protocol changes are discussed and consent is noted in the client's chart.
Step 5: Begin skill acquisition. Early sessions are about helping the client find the target state. A typical session includes a brief check-in about changes since the last visit, a short pre-training baseline, several training periods separated by rest breaks, and a debrief where the client describes what they noticed. Set thresholds to reward successive approximations, keep feedback immediate and artifact-free, and coach without over-instructing.
Step 6: Monitor learning and outcomes, and adjust. Two questions guide every review. First, is the client learning, that is, changing the trained EEG parameter within and across sessions? Second, are those changes showing up in the client's goals and daily life?
Graphing pre-session baselines, in-session performance, and symptom or goal ratings, and reviewing the graphs with the client, makes learning visible and builds motivation. A client who is not learning may need different feedback, instructions, thresholds, or session timing; a client who is learning without benefit may need a different protocol. Adjustments should also be considered if unwanted effects occur. This collaborative approach reflects one of the most important aspects of the biofeedback relationship: the trainer needs the client's active participation, and one goal of training is for the client to become a genuine partner in the process. The more informed and knowledgeable the client becomes, the more useful feedback they can provide about their experiences and how training is affecting their life.
Step 7: Build transfer and generalization. As control improves, shift the emphasis from performing well with the display to producing the state without it. Use transfer trials with feedback withheld, gradually reduce feedback, and assign between-session practice, such as the home breathing and heart rate variability training used by Clients A and B. Help the client identify real-life situations, such as a classroom, a meeting, or a tense conversation, in which to call up the trained state, and invite family members or teachers to support that practice.
Step 8: Reassess and fade. Re-evaluation is integral to the training process. A regular schedule of revisiting initial assessment tools guides protocol changes and identifies when the client has reached a plateau where no further change is likely. As goals are approached, sessions can be spaced further apart, as they were for Client B, to test whether gains hold with less support.
Step 9: Complete training and follow up. Training concludes when goals have been achieved and maintained, or when no further progress is evident. A follow-up visit a few months later, like the one planned for Client A, checks that skills are holding, and brief refresher sessions can be offered if needed. The case examples below illustrate these steps in practice.
Client Example A
This case illustrates the full assessment-to-training arc for a client with a history of traumatic brain injury (TBI). It demonstrates how qEEG findings, clinical history, and the decision-making framework converge to guide protocol selection, and how reassessment documents training outcomes.
Client A is a 38-year-old woman referred for quantitative EEG evaluation and neurofeedback training. An EEG recording session followed an initial intake and history session, during which samples of eyes-closed EEG, eyes-open EEG, and an eyes-open task condition were obtained.
Her clinical history indicated diagnoses of persistent depressive disorder and attention deficit hyperactivity disorder (ADHD). She reported attention problems, repetitive thoughts, feelings of inferiority, memory difficulties, problems making decisions, and some difficulty with communication, including word-finding and interpersonal skills. Her prenatal and birth history were unremarkable, development was typical, and she performed well academically through college, earning a BA in education before beginning a 12-year career as an elementary school teacher.
At age 25, Client A was involved in a motor vehicle accident. Although a head CT scan and skull x-ray in the ER showed no damage, she reported brief loss of consciousness and believed she struck the left lateral frontal side of her head on the driver-side window. She experienced lingering headaches for several weeks, along with neck pain and fatigue. Physical therapy helped moderately with neck pain over approximately three months but did not resolve her headaches or fatigue.
Unable to find resolution through conventional providers, she pursued alternative approaches including massage, chiropractic care, herbal medicine, and acupuncture. Chiropractic adjustments were helpful but required regular visits (2-3 times per month), and acupuncture helped with neck pain and general malaise but similarly required ongoing sessions.
At the time of assessment, she continued to report neck pain, headaches, difficulty with focus and attention, and interpersonal difficulties, symptoms she stated were not present before the motor vehicle accident.
Electroencephalographic (EEG) data were collected using the international 10-20 electrode placement system with 19 active electrodes referenced to linked ear electrodes. A NeXus-32 acquisition unit with BioTrace+ software was used for neurometric EEG collection, and all electrode locations maintained a DC offset below 25 mV. Substantial eye movement was present in both eyes-closed and eyes-open recordings, along with persistent, localized EMG artifact throughout the eyes-open recording at the F7, F8, T3, and T4 electrode locations.
Following recording, the record was visually inspected and artifact-free epochs were selected from the eyes-closed recording. However, the persistent muscle artifact made it impossible to find artifact-free segments in the eyes-open recording, so the effect of this artifact is noted in the report below. Analysis was performed using the NeuroGuide database software, comparing Client A's record to age-matched normal research participants and a discriminant function database for traumatic brain injury. Further analysis used the Key Institute LORETA database version 2003 combined with Lifespan database z-scores. This appears to be a valid and interpretable administration.
The EEG was reformatted in various referential and bipolar montages for visual inspection.
Visual Inspection of 19-Channel EEG
Eyes-Closed Condition: This fair-quality recording shows persistent EMG artifact primarily in left frontal and temporal derivations, with some presence in right frontal derivations. Typical lateral eye movement artifact appears frequently; segments containing artifacts were excluded from statistical analysis.
In the longitudinal bipolar montage, a generalized posterior dominant rhythm appears in the occipital and parietal derivations, extending somewhat to the central derivations. The frequency is approximately 9 Hz, with voltage generally in the 25-35 μV range and some bursts exceeding 50 μV at the P4-O2 derivation and 40 μV at P3-O1. Notably, the posterior rhythm is asymmetrical, with higher voltage on the right side, particularly in the T4-T6 and T6-O2 derivations.
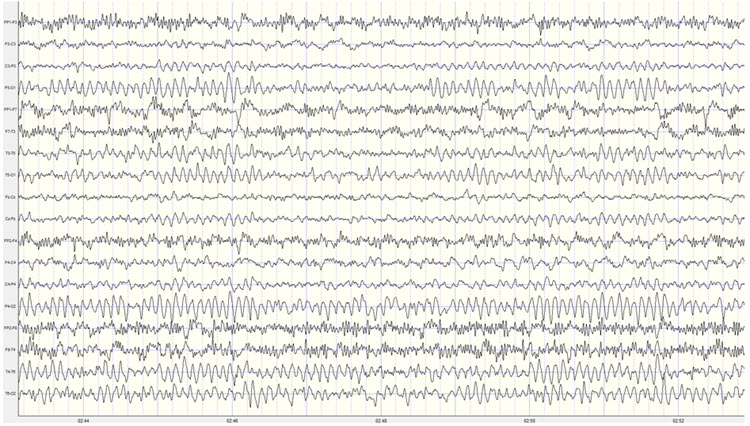
When the record was re-montaged in various bipolar derivations, additional alpha activity appeared in the temporal leads, activity that likely also appears in the ear references. This contributes to reference contamination in the linked ears montage. Bilateral frontal, temporal, parietal, and occipital slow activity in the 3-5 Hz range was also present.
The average reference montage clearly identifies the 9 Hz activity at the T6 electrode at up to 40 μV, as well as the more right-sided, O2 distribution of the posterior rhythm.
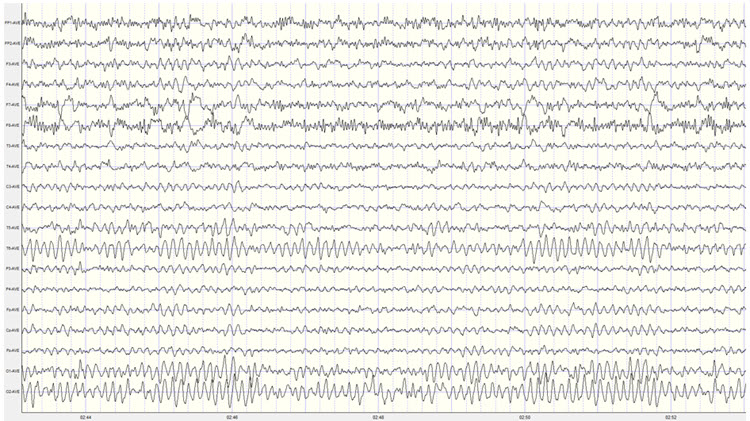
The linked ears montage shows broadly distributed alpha activity, likely the result of reference contamination from the ear references noted earlier. Consequently, elevated z-score values for frontal alpha in the linked ears statistical topographic maps should be disregarded. In this montage, the posterior rhythm appears more symmetrical bilaterally at O1 and O2, but this is likely incorrect based on the findings from all other montage views.
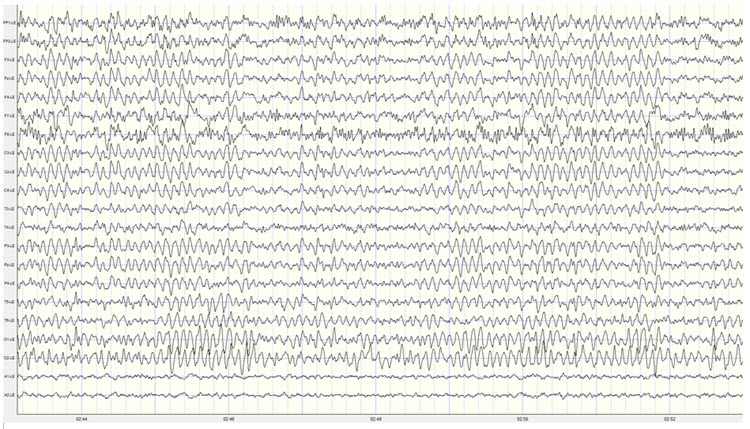
The Laplacian montage shows broadly distributed frontal and temporal EMG artifact, likely an aberration due to the reference method using adjacent electrodes for the montage calculation. Other montages localized the EMG artifact primarily to bilateral frontal and temporal derivations that did not include the F3, Fz, or F4 sensors.
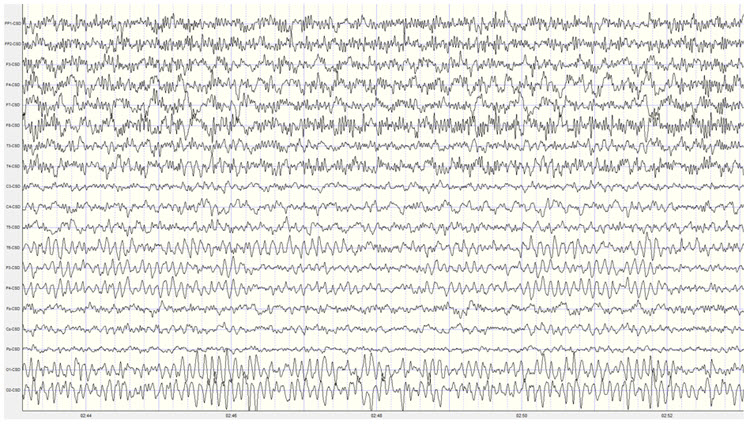
Eyes-Open Condition: The linked ears montage shows appropriate attenuation of the posterior dominant rhythm to approximately 10-15 μV. Significant muscle artifact is present in frontal and temporal leads, as noted above. Removing the low pass filter confirmed this is indeed muscle artifact rather than 60 Hz or another exogenous source. Excessive, repetitive eye blink artifact was also present, rendering this eyes-open recording unsuitable for statistical analysis.
The quantitative analysis of Client A's eyes-closed EEG record reveals the following findings:
Absolute power topographic maps of the eyes-closed average reference montage show maximum voltage in the 8-12 Hz frequency range, peaking at 9 Hz at the O2 and T6 electrode locations.
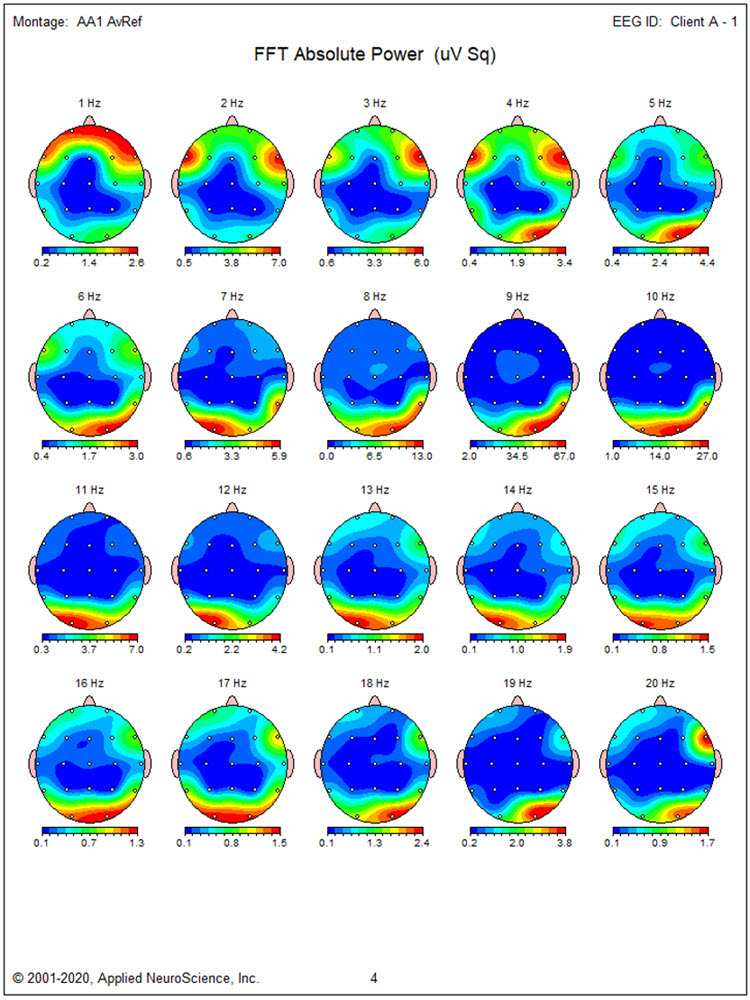
The statistical topographic maps of the eyes-closed average reference montage show the bilateral distribution of excess activity from 2-6 Hz with the greatest deviation from 2-5 Hz in bilateral frontal, temporal, right lateral parietal, and occipital electrodes. Excess activity at 9 Hz is localized to the F3, Fz, C3, and Cz electrodes and O2, T6, T4, and O1, with the greatest deviations in left central and right T6/P8 locations. Excess posterior 17-19 Hz activity and excess 17-30 Hz activity in bilateral frontal sensors are almost certainly associated with the EMG artifact noted earlier.
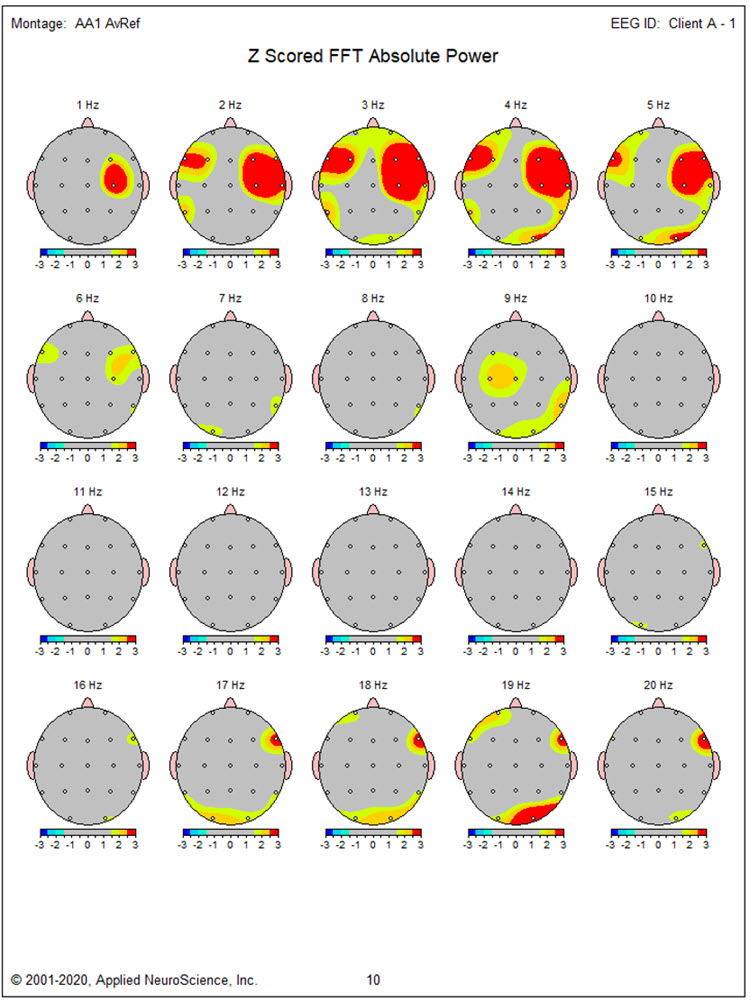
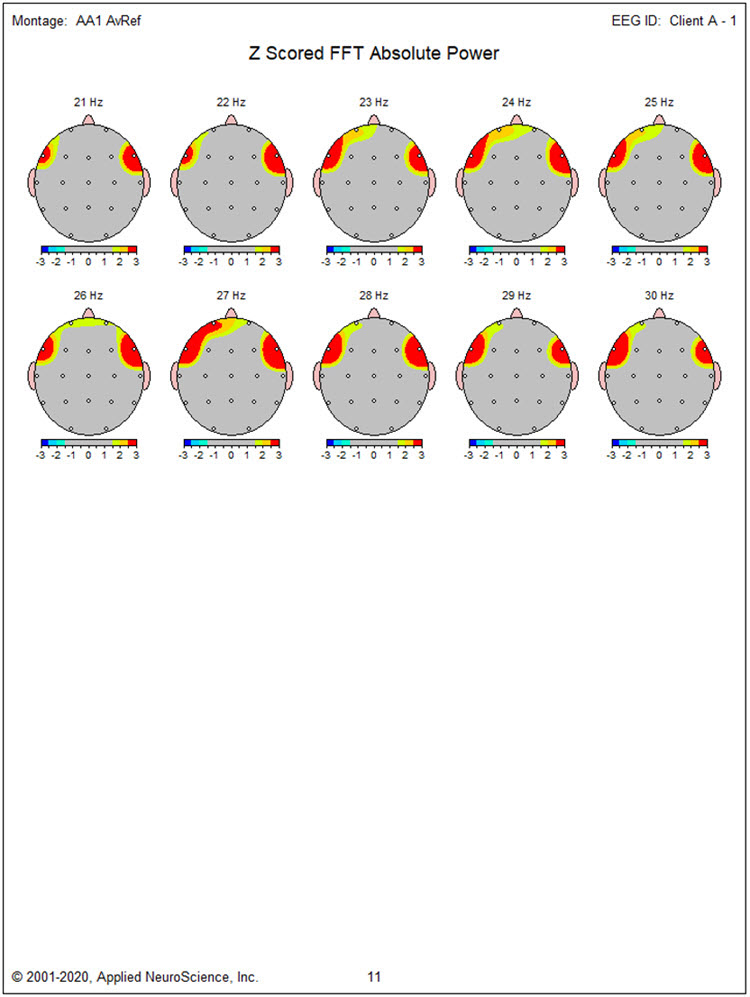
The Laplacian montage shows findings that are quite similar to those seen in the average reference montage with excess activity present from 2-9 Hz in this case. As discussed earlier, the excess fast activity is more pronounced and more broadly distributed, reflecting the EMG artifact, and should be disregarded.
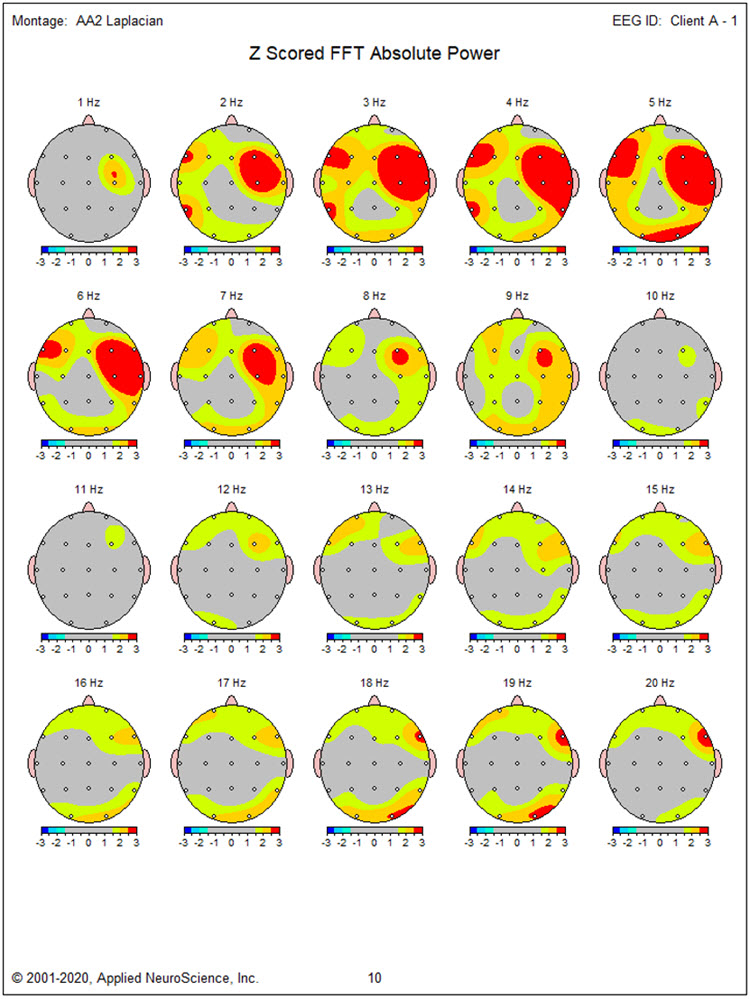
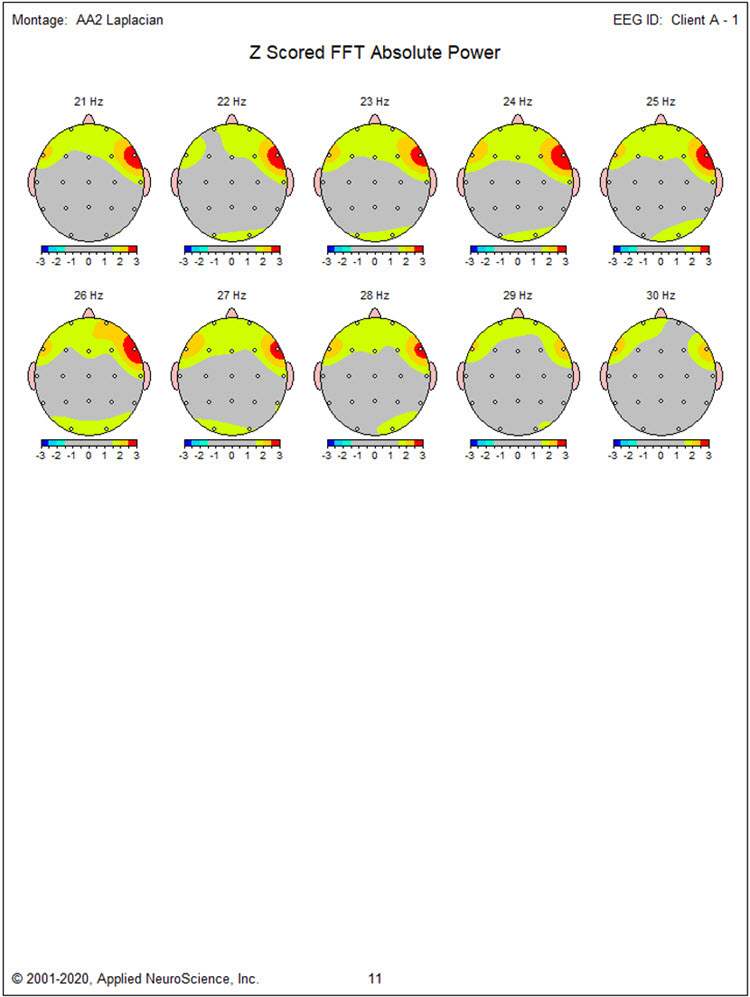
The linked ears montage shows the bilateral slow activity from 2-6 Hz that extends to the right temporal and parietal/occipital areas. The excess 9 Hz activity is more localized to the left lateral frontal and temporal areas, although this may be related to the effect of reference contamination noted earlier. The excess activity from 17-19 Hz is seen in occipital sensors, and the excess lateral frontal 17-30 Hz EMG-related activity is seen here.
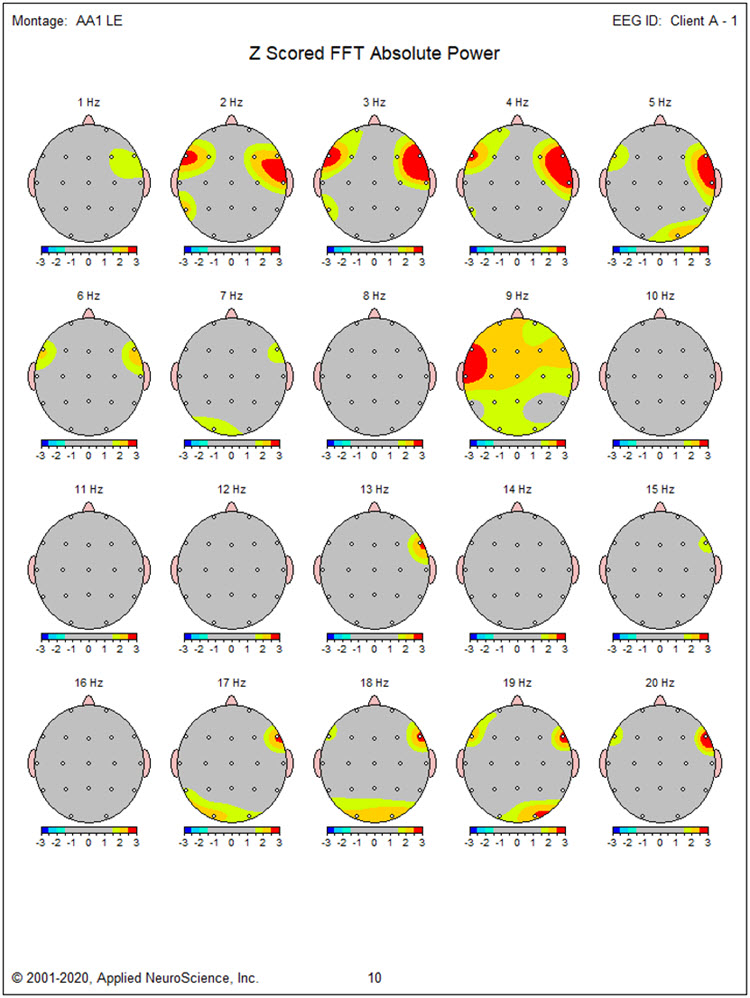
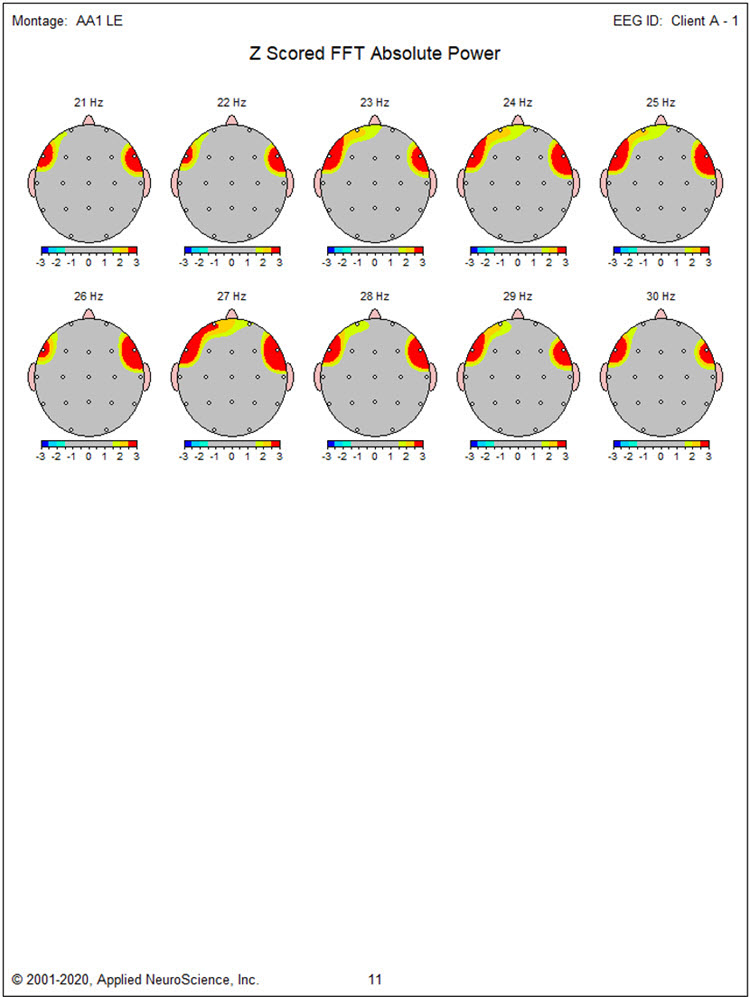
The z-scored peak frequency analysis in the linked ears montage shows some slowing of the peak alpha frequency, exceeding -1 standard deviation at C3, T3, P3, C4, T4, P4, T6, O2, and Pz, with the greatest slowing at the P4 electrode site at -1.31 SD.
Coherence abnormalities show excess frontal, central, temporal and parietal hypercoherence in the alpha frequency band with some right lateral posterior and occipital hypocoherence in the theta and alpha frequency bands. There appear to be 2 somewhat focal areas of hypocoherence in multiple frequencies at the F7 and T6 locations.
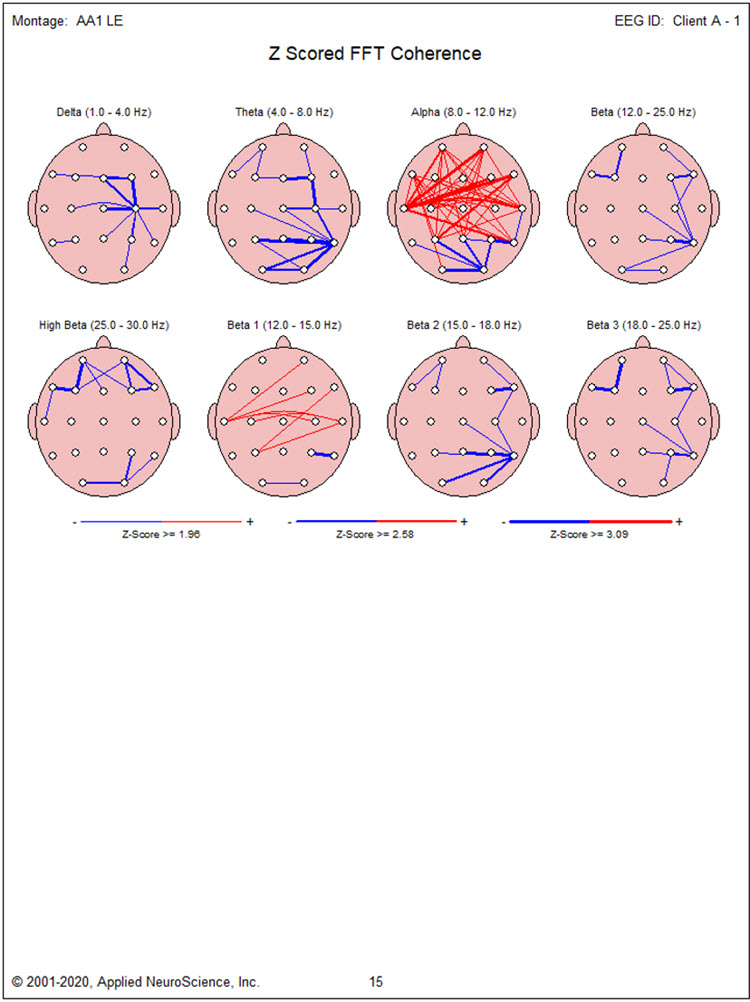
Due to the history of an automobile accident, the traumatic brain injury discriminant analysis was performed. It yielded a TBI discriminant score of 0.66, a TBI probability index of 99.5%, and a TBI severity index of 4.86, which is in the middle of the moderate range on a 0-10 scale where zero represents mild effects and 10 represents severe effects.
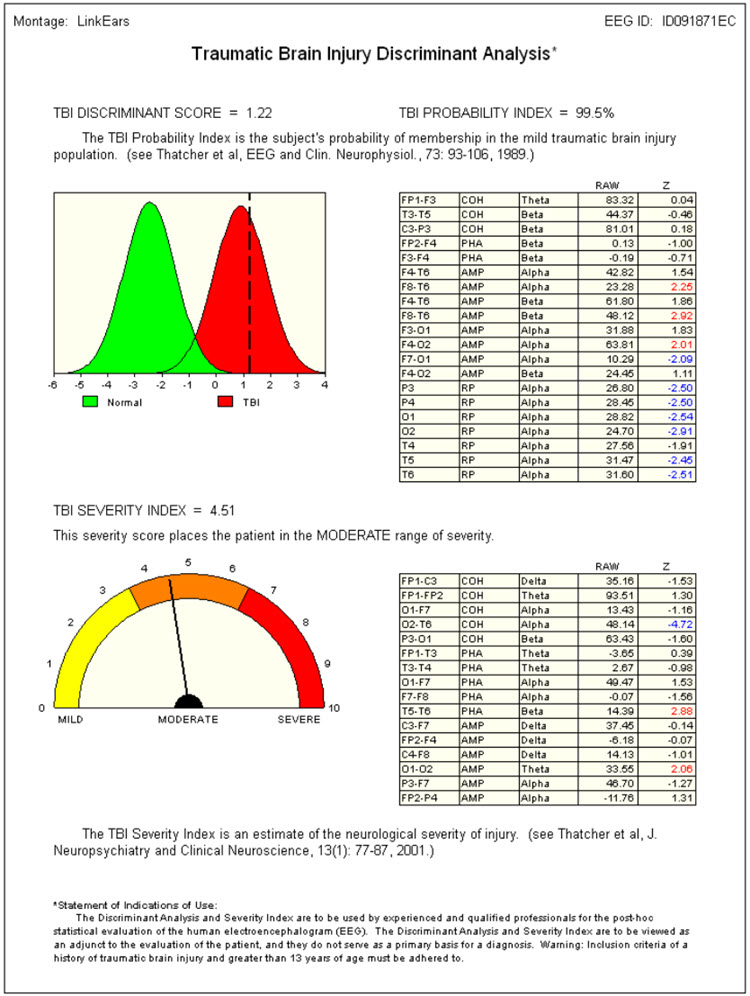
Conclusions: This client's findings suggest a possible lingering effect of the motor vehicle accident, with a pattern consistent with coup-contrecoup injury extending from the left lateral frontal area at approximately F7 to the right posterior temporal/parietal/occipital area at T4 (T8), T6 (P8), and O2. The left lateral frontal slowing may be associated with her experience of depression, the bilateral frontal slowing with her perception of attentional difficulties, and the right temporal and parietal involvement with her difficulties in social interactions.
A course of neurofeedback training is recommended, beginning with 4-channel z-score training to address these difficulties by correcting excess slow-frequency activity, normalizing coherence, and possibly resolving the slow peak alpha frequency. Initial sensor placement will be on F7, F8, T6, and O2 to normalize delta and theta frequencies, followed by O1, O2, Fz, and Pz to normalize the frequency and distribution of the posterior rhythm.
Finally, alpha-theta training, rewarding an increase in 6-9 Hz while stabilizing 2-6 Hz and 13-36 Hz, will be used to integrate changes and help resolve social anxiety. Additional home training is recommended, including heart rate variability training and peripheral temperature training with home devices. Sufficient in-clinic practice with these modalities should be provided to build familiarity with the techniques.
Disclaimer: This evaluation is not intended to diagnose any medical or psychological condition. It is also not intended to substitute for appropriate medical or psychological diagnosis and intervention. Diagnosis and medical care should rely on a physician or mental health provider. Areas that show differences from expected values and the description of common symptoms associated with dysregulation in these areas are speculative, based on current neuropsychological understandings. Descriptions may not apply to this client, and any suggested findings may need to be confirmed through other testing.
Neurofeedback Training: Client A participated in 32 sessions of neurofeedback training, scheduled 1 to 3 times weekly, and practiced daily at home with a heart rate variability respiration training device. Initial 4-channel z-score training at F7, F8, T6, and O2 encouraged all 168 z-score variables to decrease toward zero. This approach proved quite successful; her referring psychologist reported that her depression was significantly improved, along with her ability to function in day-to-day situations, particularly in terms of focus and attention.
At session 15, her symptoms and training protocols were reviewed, and the electrode locations were changed to O1, O2, Fz, and Pz because the peak alpha frequency remained somewhat depressed. This configuration was used for 5 sessions before alpha-theta training was implemented using a 2-channel sum training approach with sensors at P3 and P4 and ear references. The reward was set to encourage an increase in 6-9 Hz while inhibiting 2-6 Hz and 13-36 Hz. This eyes-closed procedure used auditory feedback and was well tolerated; she reported finding it particularly calming and helpful.
After 12 sessions of alpha-theta training, Client A decided she had achieved her goals and requested a repeat 19-channel recording to see whether her EEG reflected the changes she was experiencing in her life.
This reassessment evaluates changes in Client A's EEG to guide decisions about further training. Data were collected using the same equipment and software as before and processed in the same manner.
Client A reports significant reductions in depression, improved focus and attention, and more energy to engage with others and participate in activities. She does report feeling slightly over-activated at times, which she says reminded her of how she was before the motor vehicle accident when she was a "go getter." She can manage this occasional overactivation using the breathing and heart rate training she has practiced at home.
This is a good-quality eyes-closed recording with minimal EMG artifacts at T3 and T4. Eye movement artifact is minimal, and overall voltage is somewhat reduced from the previous recording.
When viewed in the longitudinal bipolar montage, a posterior rhythm is seen primarily in the O1 and O2 derivations with a frequency of approximately 10 Hz and amplitudes in the 15-25 μV range, with some bursts exceeding 30 μV. The voltage is more symmetrical than was seen in the previous recording, and the voltage at the P3-O1 and P4-O2 electrode derivations is quite similar. As the recording progresses, the frequency does speed up a bit to the 10-11 Hz range.
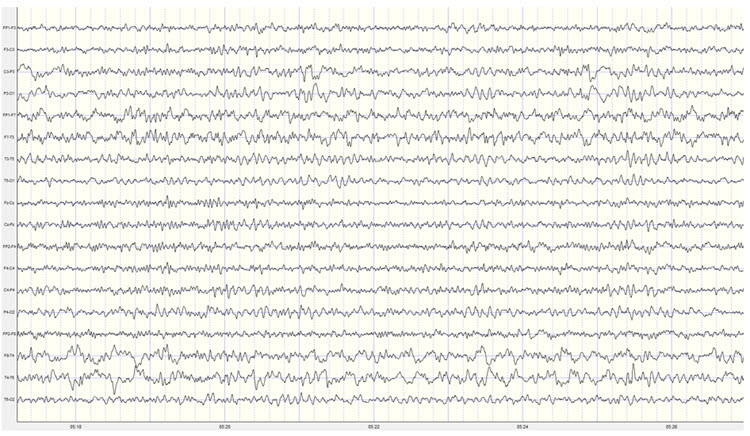
A pattern of slow activity with a frequency of approximately 3-5 Hz is seen in derivations associated with the F7, T3, P3, T4, and T6 electrodes. However, the voltage is significantly lower than in the previous recording.
The average reference montage shows the more symmetrical posterior rhythm with a 10-11 Hz frequency and amplitudes of 20-25 μV range. There is beta activity in the 15-20 Hz range in frontal and central sensors, and the slow pattern appears to be most pronounced in the F7 electrode location.
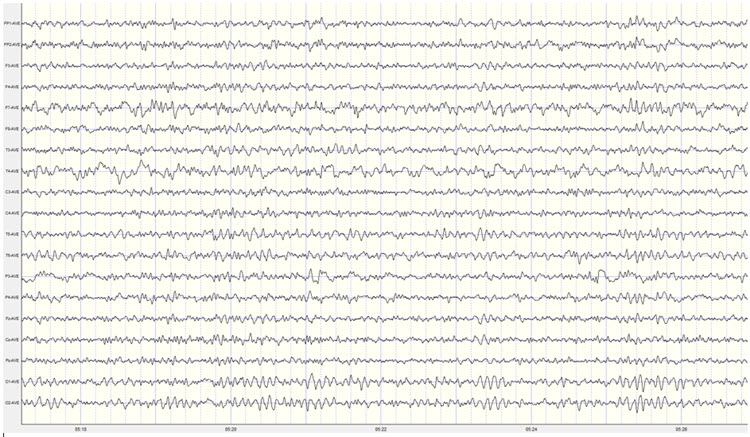
The linked ears montage continues to show reference contamination. Still, it is in the 20-25 Hz range in this case. This frequency pattern is seen in nearly every sensor at similar frequency and amplitude and with the type of phase synchrony often seen in cases of reference contamination. This contamination may be related to the EMG artifact seen in the T3 and T4 electrodes.
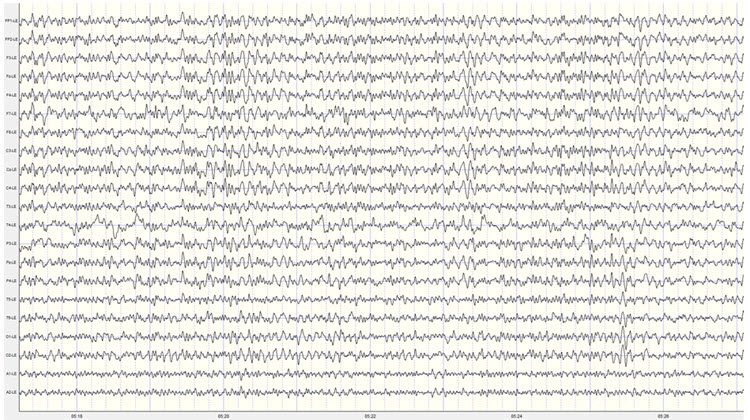
The Laplacian montage shows more EMG artifacts in the T3 and T4 electrodes than in the other montages. This montage also seems to isolate the slow activity to the F7 electrode.
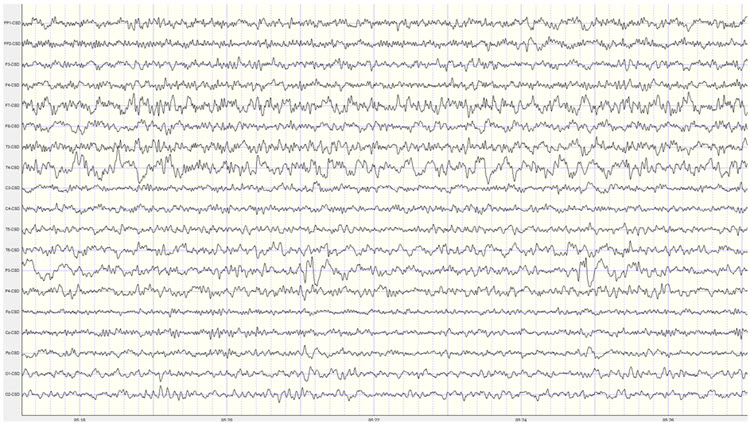
The absolute power topographic maps of the average reference montage show the more bilateral distribution of the posterior rhythm. The maximum voltage in the 8-12 Hz frequency band is at 11 Hz, closely followed by 10 Hz, though it remains somewhat lateralized to the right occipital at those frequencies.
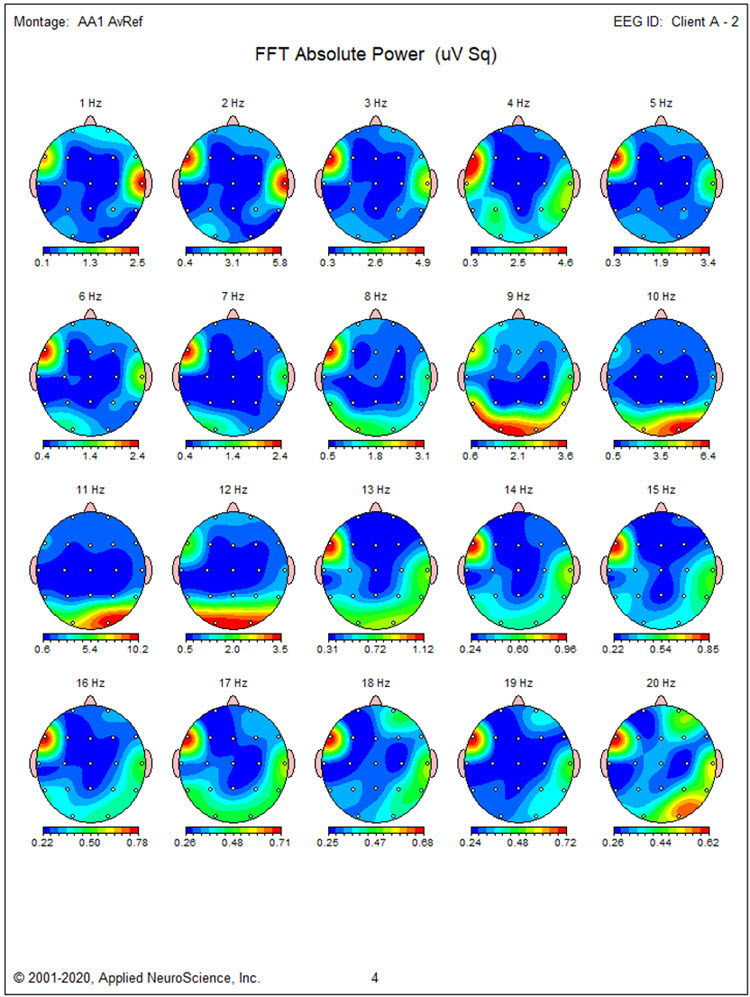
The statistical topographic maps show excess 2-6 Hz activity at F7, T3, T4, P3, P4, and T6. The distribution of excess activity is less than seen in the previous recording but remains a potential for further training to resolve the slow activity in these areas.
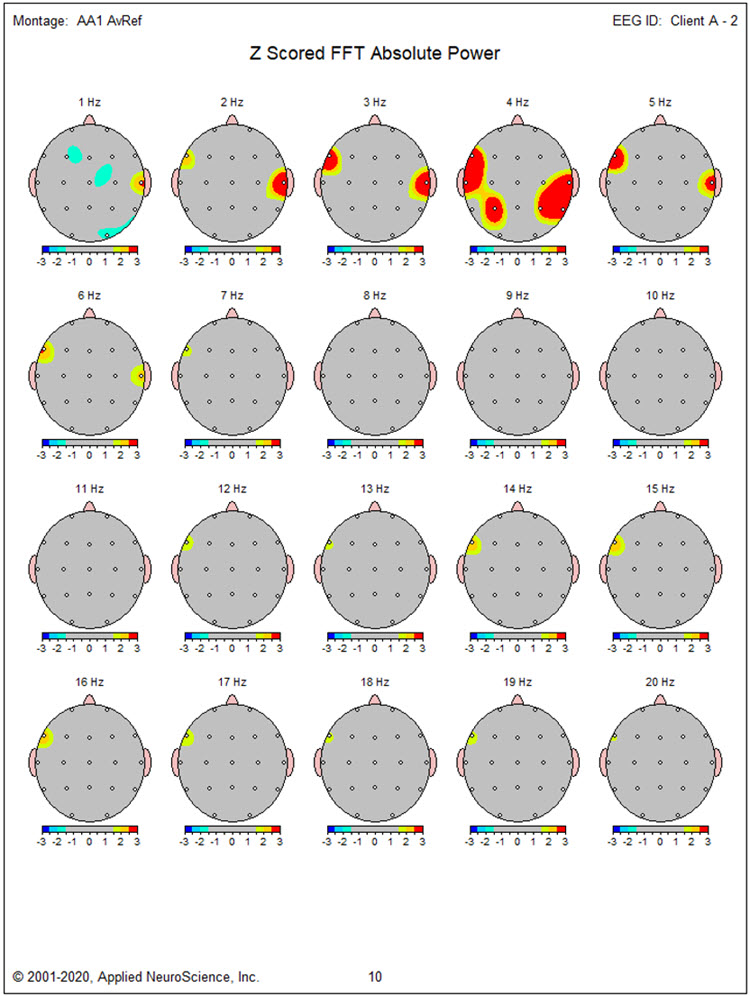
The z-scored peak alpha frequency in the linked ears montage is now more typical and shows a negative standard deviation only at C3 and C4.
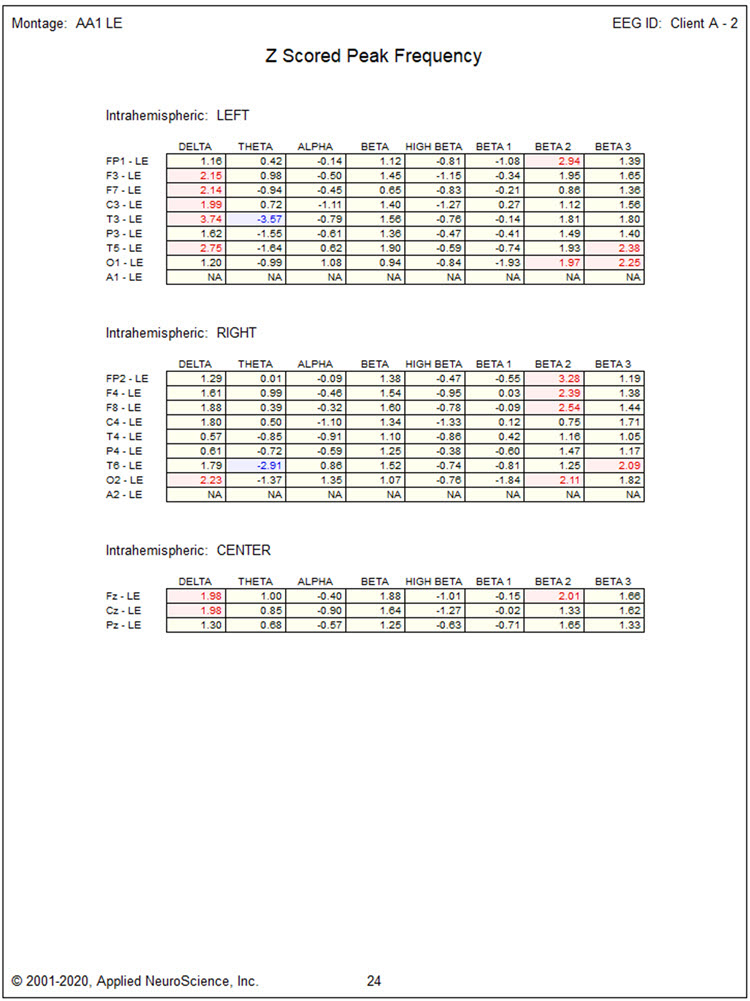
The TBI discriminant analysis surprisingly shows a non-significant value, which may be due to the reference contamination in the beta frequencies since that measure is calculated from linked ears data. It is unusual for this measure to change so drastically in so short a time, particularly when there is still significant slow activity in lateral frontal and bilateral temporal locations. It is also possible that the initial TBI finding was higher than typical given the reference contamination from slow alpha activity in the previous recording.
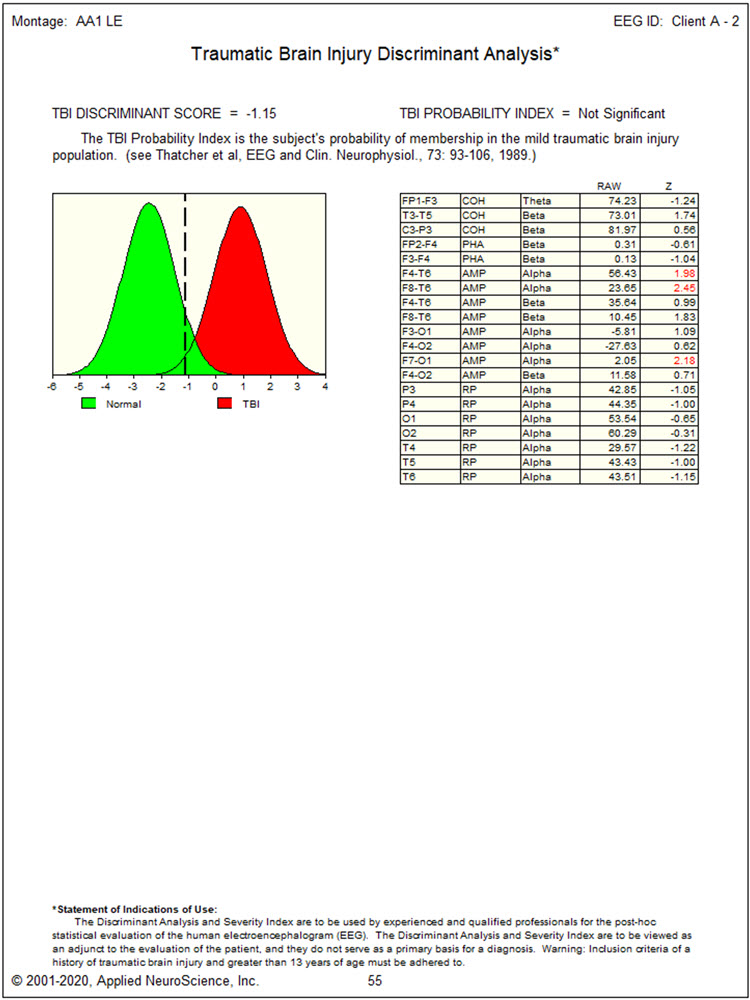
Conclusions: Client A appears to have benefited substantially from neurofeedback training combined with home respiration biofeedback practice. However, areas of slow activity remain that may be important to resolve. The increase in peak alpha frequency and her self-report of occasional overarousal may indicate a degree of overtraining that requires additional sessions to address. Because the client wishes to conclude training, she will be encouraged to return for a follow-up session in 3 months to determine whether she has achieved a more balanced state. She will also be encouraged to return for further training if she experiences negative effects, and to continue home training with the HRV device.
Disclaimer: This evaluation is not intended to diagnose any medical or psychological condition. It is also not intended to substitute for appropriate medical or psychological diagnosis and intervention. Please see your physician or mental health provider for appropriate diagnosis and medical care. Areas that show differences from expected values and the description of common symptoms associated with dysregulation in these areas are speculative based on current neuropsychological understandings. Descriptions may not apply to this client, and any suggested findings may need to be confirmed through other testing.
Client Example B
This case involves a former college football player with a history of multiple head injuries. It illustrates how neurofeedback protocol selection adapts when TBI is longstanding and the client presents with a complex mix of cognitive, emotional, and interpersonal symptoms.
Client Information
| Name: Client B | Date: 02/20/2014 |
| Exam#: Client B 10001 | Ref. By: Self |
| Age: 57.51 | Test Site: MNI |
| Gender: Male | Handedness: Left |
Recording
| Analysis Length: 01:42 | Ave. LE Split-Half Reliability: 0.98 |
| Ave. LE Test-Retest Reliability: 0.94 | Eyes: Closed |
Medication: None noted
History: Client B presents with a diagnosis of traumatic brain injury (TBI) from multiple head injury events during high school and college football. During his college career, he sustained one particularly significant injury from helmet-on-helmet impact to the left lateral frontal area, resulting in approximately 10 minutes of loss of consciousness followed by confusion and dizziness. He returned to the game in the second half after sitting out the rest of the first half, a decision that would not meet current concussion protocols. Lingering symptoms persisted through the following summer after graduation, and although they faded over time, he reports never feeling that he returned to his "normal self." He nonetheless became a successful businessperson.
He reports persistent depression with a lack of motivation and a significant struggle to function in daily activities. He also describes a "temper" that has cost him several relationships; he is currently divorced from his third wife and believes his mood regulation problems are primarily responsible. Symptoms endorsed include depression, headaches, feelings of loneliness, memory problems, occasional dizziness, mild to moderate general anxiety, some fear or panic experiences, difficulties with sequential processing, emotional sensitivity, social discomfort, problems falling asleep and restless sleep, slow processing and response, poor reading comprehension, difficulty understanding concepts, and a lack of well-being.
Visual Inspection of 19-Channel EEG
Eyes-Closed Condition: Longitudinal Bipolar Montage: this is a good quality recording with moderate eye movement artifact and only intermittent movement and EMG artifact. There are no discernable mains or equipment artifacts.
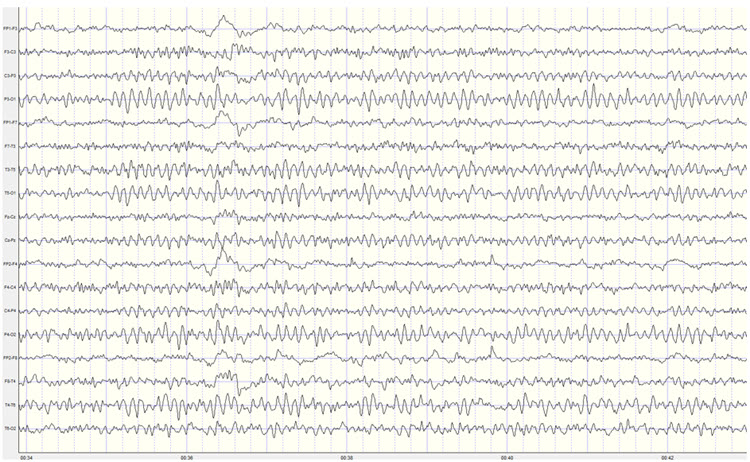
The longitudinal bipolar montage shows a clearly defined posterior rhythm in derivations including temporal, parietal, and occipital electrodes. The frequency of the posterior rhythm appears to be somewhat inconsistent and ranges from 8-10 Hz. Amplitudes are generally in the 10-15 μV range with bursts up to 40 μV, occasionally exceeding 55 μV.
There is a clear pattern of slow activity in left lateral frontal derivations that include the Fp1-F3, Fp1-F7, F7-T3, and T3-T5 electrodes. There is also what appears to be a corresponding area of slow activity in the right temporal and temporal-parietal derivations. There is beta activity frontally in the 15-20 Hz range.
There is a period of apparent light or stage one sleep in the middle of the recording, interspersed with brief awakenings. The EEG shows occasional vertex sharp waves but no other sleep characteristics. This pattern resolves, and Client B returns to an awake eyes-closed state for the rest of the recording.
The average reference montage also shows a well-developed posterior rhythm with the maximum voltage in the O1 and O2 electrodes, with additional posterior rhythm activity at T5, T6, P3, and P4. The voltage at T6 is nearly as high as in occipital sensors. The frequency continues to fluctuate between 8-10 Hz, and voltage is in the 10-20 μV range with bursts regularly exceeding 40 μV and occasionally 50 μV.
A pattern of slow activity is seen in this montage as well, with the clearest and most consistent activity in the left and central frontal, left central, right frontal, and right parietal and occipital areas, with frequencies varying between 2 and 4 Hz. There is also some alpha activity in frontal sensors, particularly at F3 and Fz.
The Laplacian montage also shows the posterior rhythm in occipital and parietal areas and shows a mixed pattern of activity at the T4 and T6 electrodes, with slower activity in the delta and theta frequencies mixed with alpha and beta frequencies. Left-sided slow activity is also seen.
The linked ears montage shows broadly distributed alpha activity suggesting reference contamination. The highest voltage of the posterior rhythm is in the occipital electrodes. There is alpha activity in the reference electrodes and a pronounced ECG artifact that will likely produce excess 1 Hz statistical values in the z-score analysis. This should be disregarded.
The sequential eyes-open, eyes-closed recording shows a typical alpha response upon eyes closing and appropriate alpha blocking upon eyes opening in this repetitive series of 15-30 second eyes-open and eyes-closed segments (see image below).
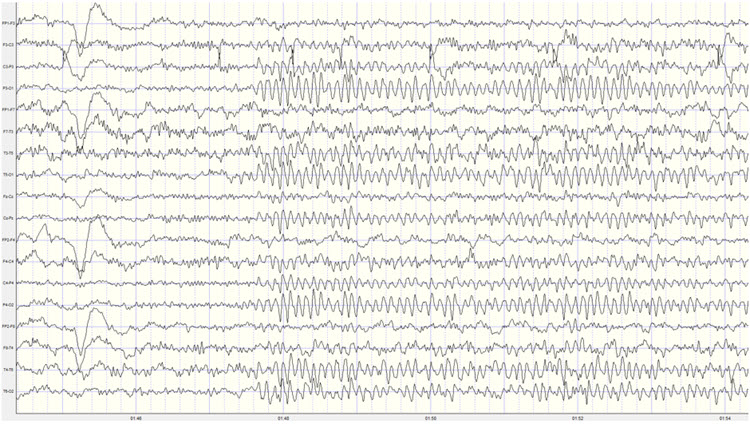
Eyes-Open Condition: Visual inspection of the eyes-open longitudinal bipolar montage recording shows appropriate attenuation of the posterior rhythm upon eyes opening.
Background activity shows mixed frequencies, including delta, theta, and beta frequencies. Beta frequencies are in the 20-30 Hz range. Alpha intrusions are also seen quite often in central-parietal, temporal-parietal, and parietal-occipital derivations. The slow patterns noted earlier are seen in frontal-central, central-parietal, and right-sided temporal-parietal and parietal-occipital derivations.
The average reference montage shows more widely distributed alpha activity throughout the recording, possibly due to the generalizing effect of averaging all electrodes for the reference. Otherwise, the findings are consistent with the longitudinal bipolar montage.
The Laplacian montage shows the alpha activity mostly in occipital areas and the mixed slow and fast activity in the T6 electrode noted in the eyes-closed recording.
The linked ears montage shows a generalized pattern of 9-10 Hz activity mixed with beta and theta frequencies.
The LORETA z-score analysis shows broadly distributed 1-Hz activity which is expected due to the ECG artifact, and also shows the lateralized left frontal and right posterior temporal/parietal areas as exceeding 2 standard deviations at 2-6 Hz, as well as right lateral frontal 9 Hz activity exceeding 2 standard deviations (see LORETA images below).
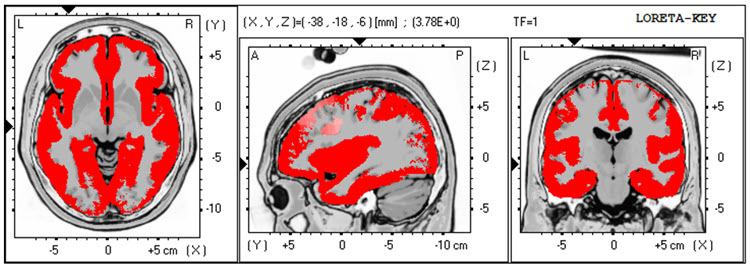
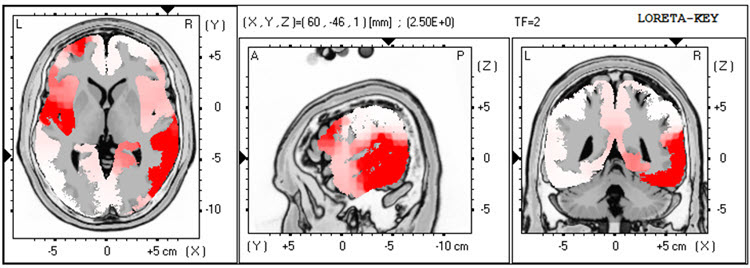
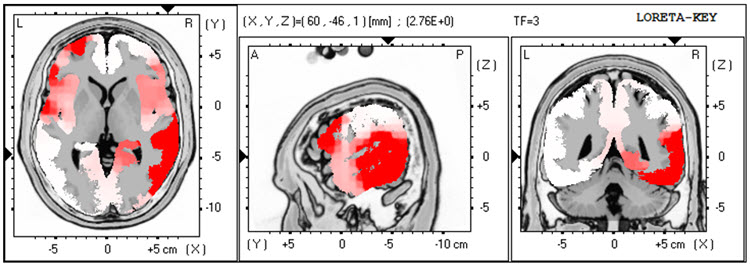
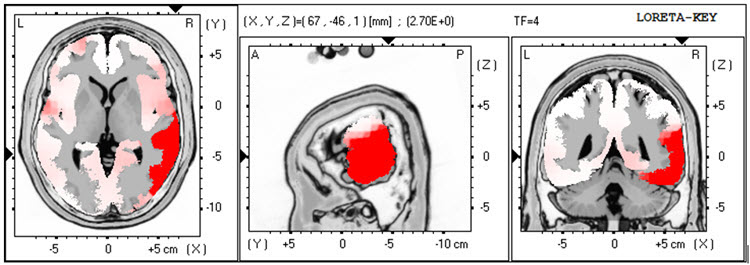
Quantitative Analysis: The analysis of the absolute power topographic maps of the average reference montage of the eyes closed recording shows the maximum of the 8-12 Hz frequency band to be at 9 Hz in bilateral occipital electrodes, followed by 10 Hz at approximately half the power. (These maps display power in μV2; power is amplitude squared, so power and amplitude differences are not interchangeable.) There is a clear right posterior temporal/parietal activity distribution from 2-15 Hz, reflecting the visual inspection findings.
The statistical topographic maps of the eyes closed average reference montage show broad distribution of 2.5-3 SD activity at 1 Hz, associated with the ECG artifact noted earlier, and this should be disregarded. There is excess activity in Fp1, F7, C3, Fz, F4, T4, T6, Pz, O1, and O2 electrodes from 2-3 Hz, with lesser, mostly right parietal and posterior excess from 4-5 Hz. The greatest deviation is at the F4, T6, and O2 electrodes exceeding 2.5-3 SD.
There is also excess bilateral frontal and left frontal/central and right parietal/occipital 9 Hz activity with the greatest deviation between F3, Fz, C3, and Cz. There are moderate excess occipital and right parietal 12-14 Hz activity and some 19-22 Hz excesses.
The peak alpha frequency is slightly slow but does not exceed -1 SD at any location.
The Laplacian montage shows the 1 Hz activity related to the ECG artifact. This montage shows the maximum deviation from 2-5 Hz at T6 with lesser deviations in the left lateral frontal, frontal, central, parietal and occipital areas. The excess 9 Hz is seen here, with some minimal 13-14 Hz activity in the right occipital and parietal areas.
The linked ears montage shows more distribution and greater deviation in most frequencies noted previously. Interestingly, the excess slow activity shows a much more lateralized presentation than was seen in the other montages. This may be due to reference contamination, and it could be coming from the area of the T4 and T6 electrodes, which are near the right-sided reference.
Coherence abnormalities are pronounced, but this is likely not reliable due to reference contamination in the linked ears montage.
Due to the reports of multiple impact injuries to the head, the Traumatic Brain Injury Discriminant Analysis was performed. It yielded a TBI discriminant score of -0.43, a TBI probability index of 80.0%, and a TBI severity index of 5.44, which is in the moderate range on a 0-10 scale, where 0 represents mild severity and 10 is severe.
Conclusions: This client presents with multiple issues that may relate to the observed EEG findings. The slow activity in left frontal areas and the combination of slow activity plus higher-than-typical alpha amplitude in right posterior temporal/parietal areas are particularly noteworthy. Although the peak alpha frequency slowing is not statistically significant, normalizing this frequency may improve his cognitive function.
Recommendations: A course of neurofeedback training is recommended, beginning with 4-channel z-score training that rotates between electrode combinations: Fz, Pz, T3, and T4 first; then F3, F4, T5, and T6; followed by C3, C4, P3, and P4. Other protocols may be explored as training progresses.
Summary of Client Responses to Training: Client B completed 25 sessions of neurofeedback training over 15 months, scheduled weekly at first and less frequently during the second half of that period. He also used a home heart rate variability training device and an audiovisual entrainment (AVE) device. Session training included 6 sessions at Fz/Pz/T3/T4, 2 sessions at Fz/Pz/P3/P4, 11 sessions at T5/T6/O1/O2, and 1 session at F3/F4/P3/P4, all using 4-channel z-score training. He also received 2 sessions of 4-channel slow cortical gradient training and 3 sessions of C3/C4 2-channel difference and sum training with variable reward frequency. Alpha-theta training was attempted on a few occasions, but he did not find it agreeable, so training was changed within those sessions to one of the other protocols.
He reports significant improvement in his ability to focus and in mood regulation. He is in a new relationship and states that his temper is much more manageable, having learned improved communication skills through couples counseling with his current significant other. He notes increased energy, improved sleep, and better cognitive function. Headaches still occur occasionally but with markedly decreased intensity and duration. Feeling that he has resolved his presenting concerns, he requested a follow-up EEG to see whether the assessment would reflect the changes he is experiencing.
Second Recording
| Analysis Length: 01:32 | Ave. LE Split-Half Reliability: 0.97 |
| Ave. LE Test-Retest Reliability: 0.94 | Eyes: Closed |
Visual Inspection of Follow-Up 19-Channel EEG:
Eyes-Closed Condition: Visual inspection of the 19-channel EEG in the eyes closed condition using the longitudinal bipolar montage shows a good quality recording with typical eye movement artifact and some brief episodes of what appears to be drowsy or light sleep activity. There is no evidence of EMG artifact, mains, or other exogenous artifacts in this recording. This recording appears to be significantly lower in amplitude than the previous recording.
A well-developed posterior rhythm is seen primarily in parietal and occipital derivations with some temporal-parietal and central-parietal derivations. There is some spindling beta activity seen with the frequency of 20-25 Hz. This occasionally occurs in frontal-central derivations. There is some slow activity in the left lateral frontal areas and the right posterior temporal/parietal areas.
The posterior rhythm shows a consistent frequency of 9 Hz with a well-developed sinusoidal rhythm and amplitudes generally in the 20-30 μV range, with occasional bursts exceeding 30 μV. The posterior rhythm appears quite symmetrical between left and right locations, with the maximum voltage in parietal-occipital derivations.
The average reference montage shows more generalized alpha activity, possibly suggesting some distribution associated with the averaging method of the montage. The posterior rhythm is seen with the highest voltage at O1 and O2, closely followed by T6. The frequency remains at 9 Hz and is quite consistent, with amplitudes in the 20-30 μV range occasionally exceeding 30 μV. Again, the periods of possible drowsiness or light sleep are seen that occur quite infrequently and do not persist for any length of time.
The Laplacian montage also shows the posterior rhythm in occipital sensors and right parietal T6 and lateral parietal P3 and P4 locations. There is beta activity in the 15-25 Hz range in frontal and central sensors, and there is some slow activity in left-sided frontal and right-sided parietal areas.
The linked ears montage shows widespread alpha activity in all sensors, including the bilateral reference channels, and therefore reference contamination is present.
When viewed in the longitudinal bipolar montage, the repetitive eyes-open and eyes-closed segments show a clear alpha response upon eyes closing and immediate alpha blocking upon eyes opening (see example below).
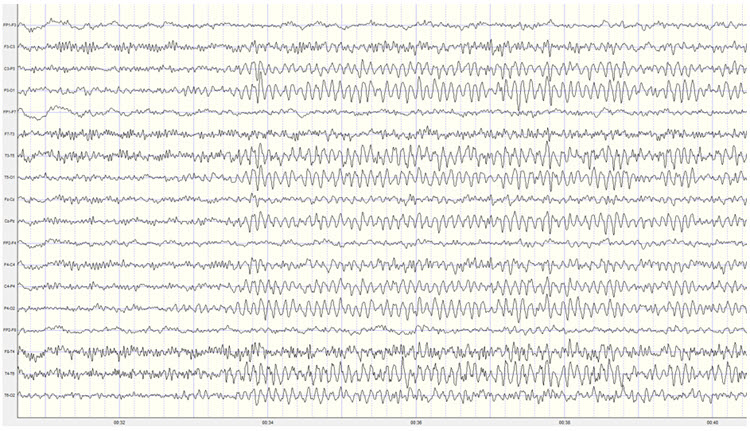
Eyes-Open Condition: Visual inspection of the eyes-open longitudinal bipolar montage recording shows appropriate attenuation of the posterior rhythm with typical eyeblink and eye movement artifact. There is beta activity in the 15-25 Hz range in all electrode derivations. There are occasional alpha intrusions into the eyes-open recording, although these are infrequent and do not persist.
The average reference montage shows essentially the same findings though there is some persistent mixed frequency activity in the T4 and T6 electrodes, with alpha and beta frequencies occurring simultaneously.
The Laplacian montage shows higher amplitude mixed frequency activity at the F7 electrode and T4 and T6 electrodes. This activity includes a pattern of activity at approximately 8-9 Hz, 13 Hz, and also at 23 Hz.
The linked ears montage again shows broadly distributed activity that is quite synchronous and likely represents reference contamination.
LORETA analysis of the follow-up 19-channel EEG recording shows the same lateralization exceeding 2 standard deviations seen in the previous recording, but in this case, only seen at 1 Hz in the left lateral frontal and right temporal areas. This activity is not seen at 2-3 Hz, and there is an area of excess activity in the right temporal area at 4 Hz, again exceeding 2 standard deviations. There is minimal excess activity at 9 Hz in the bilateral inferior temporal, fusiform, and parahippocampal gyri. (See LORETA images below).
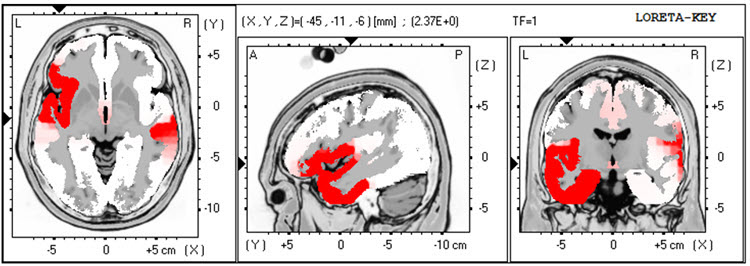
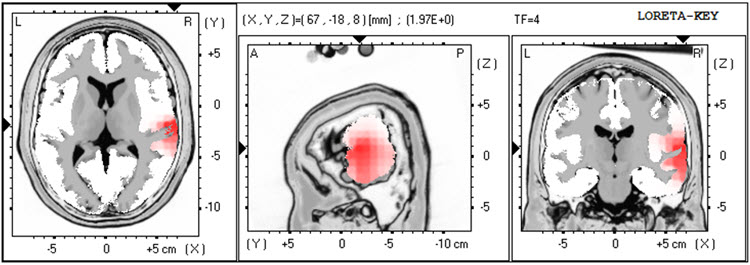
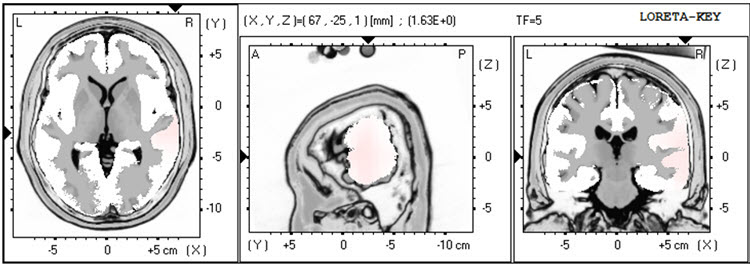
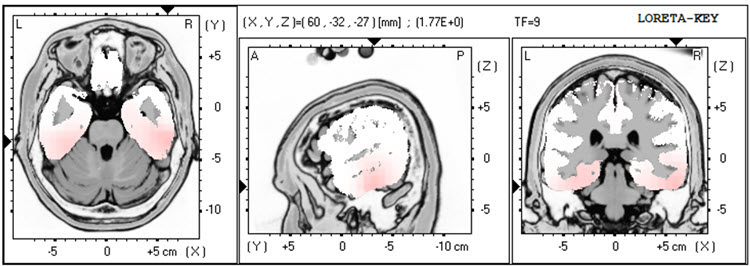
Analysis of the eyes-closed average reference montage absolute power topographic maps from the 2nd recording shows the maximum in the 8-12 Hz frequency band at 9 Hz, with a power value approximately two-thirds of that seen in the previous recording.
The statistical analysis of the absolute power topographic maps in the average reference montage of the eyes-closed recording shows excess activity exceeding 2 standard deviations at F7 and T4, with lower levels of deviation at Fp1, F8, Cz, C4, and T6. Additional activity areas exceed 2 standard deviations at 2 and 3 Hz at T4 and T6. There is excess activity in the 1-1.5 standard deviation range in the left frontal and central areas and the bilateral posterior, including T6, and finally, a small area of excess activity at 13 Hz at T6 and O2. These findings are significantly diminished from the previous recording and likely reflect behavioral experience changes. Some areas of excess activity from 21-23 Hz appear associated with the Fz electrode, which will be evaluated further in other montages.
The peak alpha frequency remains within the normal range in all locations and only exceeds a -1 standard deviation at the T4 electrode location.
The Laplacian montage essentially shows the same findings except for the right temporal/parietal area activity extending up to 5 Hz and the excess 9 Hz activity in more circumscribed locations. Also, the excess 21-23 Hz activity is associated with the Cz electrode, and therefore that seen in the average reference more broadly distributed is almost certainly due to reference contamination from the averaging mechanism in that montage.
As expected, the linked ears montage shows a broadly distributed excess activity pattern from 6-15 Hz across frontal areas reflecting the reference contamination noted earlier. Otherwise, it also shows the laterality seen in the previous recording from the left lateral frontal to the right temporal, possibly related to reference contamination.
The comparison to the previous traumatic brain injury discriminant analysis shows very similar findings, with the TBI discriminant score at -0.03, the TBI probability index at 90%, and the TBI severity index at 5.42, which is similar to that seen previously.
Conclusions: The quantitative findings are substantially improved and support his self-report of improvement in multiple areas of functioning, although the TBI discriminant measures are essentially unchanged. Client B was encouraged to return for further sessions if problematic symptoms increase, to continue heart rate variability training at home, and to continue using the audiovisual entrainment device (AVE).
Summary and Conclusion
This unit has presented a systematic, evidence-based framework for developing neurofeedback protocols. The approach is data driven. Initial protocols are chosen on the best available evidence, and we judge whether they are working by measurable changes once training is underway. Just as important, the client is closely involved from the start, which builds the ethical principles of autonomy and informed consent into every step of the decision-making process.
The framework begins with ruling out functional causes through collaboration with integrative medicine professionals, then proceeds through assessment, protocol selection, training, ongoing monitoring, and reassessment. The two client examples illustrate how this process unfolds for clients with traumatic brain injury and its effects on mood, attention, and relationships. In each case, the intersection of the client's symptoms, EEG findings, and research evidence guided protocol selection, and when initial approaches fell short, the framework provided a principled basis for adapting the training plan.
Underneath every step is a simple idea: neurofeedback is training. Clients learn to regulate their own brain activity through feedback-based learning, guided by a trainer who provides immediate, contingent feedback, shapes performance in planned steps, monitors learning, and builds transfer into everyday life. There is nothing magic about it. Framing the work this way sets realistic expectations, invites the client to be an active partner, and helps explain why well-learned gains can last after training ends.

Protocol development follows a systematic, evidence-based approach that integrates six key factors: the client's condition and goals, research findings, practitioner expertise, available resources, environmental context, and client values. The process starts with screening for functional causes through integrative medicine collaboration, then moves through assessment, protocol selection, training, ongoing monitoring, and reassessment. The two client examples demonstrate how this framework applies to clients with traumatic brain injury and accompanying depression, attention problems, and mood dysregulation, always grounding decisions in the convergence of symptoms, EEG findings, and research evidence.
Functional and Integrative Medicine Collaboration
A growing body of evidence shows that psychiatric and neurological symptoms may stem from functional causes, including environmental toxins, infections, and gut-brain axis dysfunction. This recognition represents a paradigm shift in neurofeedback practice. Swatzyna and colleagues (2024) advocate for routine screening of EEG biomarkers such as focal slowing, spindling excessive beta, encephalopathy, and isolated epileptiform discharges. When these biomarkers appear alongside new or worsening symptoms, clinicians should partner with functional and integrative medicine professionals to identify and address underlying causes before initiating neurofeedback. For practitioners in VA settings, hospitals, and clinics, this means developing referral networks with specialists who can investigate environmental and metabolic contributors to cases that have not responded to prior interventions.
Advances in Z-Score Neurofeedback and swLORETA
The continued refinement of swLORETA source localization methods has enhanced the precision of 19-channel z-score neurofeedback training. With a growing literature, though one still short of randomized controlled trials, z-score neurofeedback offers practitioners the ability to target specific Brodmann areas, cortical structures, and brain networks with increasing individualization. These advances are particularly relevant for practitioners working with complex presentations, such as TBI or multi-symptom cases, where network-level dysfunction demands protocols that go beyond single-channel amplitude training.
Learning Theory and the Training Model
Kerson et al. (2026) revisited the learning-theory framework first set out by Sherlin et al. (2011). Their update re-emphasizes tightly timed feedback, careful threshold setting and shaping, continuous reinforcement during clinical training, and transfer trials, and it describes learning as moving from explicit strategy use toward implicit learning and interoceptive awareness. They also note that a client's trust in the process and in the trainer can act as a secondary reinforcer, a reminder that the training relationship matters. Consensus reporting standards for neurofeedback research (CRED-nf; Ros et al., 2020) likewise ask investigators to report whether participants actually learned to regulate the target signal, a standard that applies equally well to clinical records.
Check Your Understanding
- What are the key "red flags" that should trigger a referral to a functional or integrative medicine professional before starting neurofeedback?
- Describe the three levels of analysis (biological, psychological, socially significant behavior) used to establish training goals, and give an example of each.
- Explain how the decision-making flowchart guides protocol selection when a research-based protocol proves ineffective for a particular client.
- Why is the collaborative relationship between clinician and client considered essential throughout the neurofeedback training process?
- In Client Example A, how did the qEEG findings guide the choice and sequence of training protocols, and what did the reassessment show?
- Why is neurofeedback better described as training than as treatment, and how does this framing change the roles of the client and the practitioner?
- Name three learning principles that should shape every neurofeedback session, and explain how transfer trials help clients carry new self-regulation skills into daily life.
- How does Othmer's endogenous neuromodulation model differ from the operant learning model in its explanation of how neurofeedback works and in how training is conducted? What do the two views share?
Assignment
Now that you have completed this unit, explain the roles of neuroscience and peer-reviewed outcome studies in developing neurofeedback protocols. In your response, discuss how brain-behavior relationships inform electrode placement, how efficacy research guides initial protocol selection, and what the practitioner should do when a research-supported protocol proves ineffective for a particular client. Finally, describe how learning principles shape the steps of the training process, from orienting the client through transfer, generalization, and follow-up.
Glossary
alpha 1 (low alpha): a protocol-dependent subdivision of the alpha band, commonly 8 to <10 Hz; proposed functional interpretations are not universal.
alpha 2 (high alpha): a protocol-dependent subdivision of the alpha band, commonly 10 to <13 Hz; proposed functional interpretations are not universal.
alpha asymmetry neurofeedback for mood disorders: a neurofeedback protocol intended to modify the left-right frontal alpha-power relationship, usually toward relatively greater left frontal activation; efficacy and optimal parameters remain unsettled.
alpha rhythm: an 8 to <13 Hz EEG rhythm dominant posteriorly during relaxed wakefulness with eyes closed and attenuated by eye opening.
alpha spindles: waxing-and-waning bursts of alpha-frequency EEG activity.
amplitude: the magnitude of a signal's excursion from a specified reference level, reported using a stated convention such as peak, peak-to-peak, or RMS.
autoimmune encephalitis: an inflammatory brain disorder in which the immune system attacks healthy neural tissue, producing confusion, seizures, memory loss, psychiatric symptoms, and behavioral change.
base rate: the prevalence of a condition or symptom in the population being served, before any sign, symptom, or test result is considered; it sets the prior probability against which new evidence is weighed.
beta rhythm: a 13 to <30 Hz EEG rhythm, usually low amplitude, associated with alert wakefulness and active cognitive or motor processing.
beta spindles: trains of spindle-like waveforms, most often frontocentral, with a reported mean frequency of 20.6 Hz (SD = 4.1 Hz) spanning roughly 14-30 Hz. They may signal ADHD, especially with tantrums, anxiety, autism spectrum disorder (ASD), epilepsy, and insomnia.
binary feedback: feedback that is either on or off, signaling only whether the trained EEG parameter has crossed a threshold; it gives no information about performance below the threshold.
Broca's area: the area located in the inferior frontal gyrus (BA 44 and 45) of the dominant hemisphere (F7-T3 in the left hemisphere) concerned with speech production, grammar, language comprehension, and sequencing.
Brodmann area (BA): a numbered cytoarchitectural zone of the cerebral cortex mapped by Brodmann from Nissl staining; the numbering runs to 52, but areas 12-16 and 48-51 were defined in non-human species.
chronic inflammatory response syndrome (CIRS): a proposed multisystem diagnosis attributed to biotoxin exposure that is not recognized as a standard diagnosis by major consensus classification systems.
cognitive bias: a systematic error in judgment that arises from a mental shortcut or heuristic, such as anchoring on an initial diagnosis, overconfidence, relying on readily available evidence, or persisting because of effort already invested.
connectivity training: neurofeedback in which feedback depends on a specified relation between signals at two or more sites, such as coherence, phase, or amplitude covariation.
default mode network (DMN): a cortical network of sites located in frontal, temporal, and parietal regions that is most active during introspection and daydreaming and relatively inactive when pursuing external goals.
delta rhythm: a 0.5 to <4 Hz EEG rhythm in the tutorial convention, prominent during N3 sleep and potentially abnormal when focal or excessive in awake adults.
diffuse encephalopathy: widespread cerebral dysfunction, usually manifested by altered cognition or consciousness and caused by toxic, metabolic, infectious, inflammatory, hypoxic, or other systemic processes.
dominant frequency: the frequency with the greatest specified amplitude or power within a signal or spectrum.
endogenous neuromodulation: Othmer's term for the brain's self-directed regulation in response to continuous feedback of its own activity, proposed as an alternative to operant conditioning as the mechanism of neurofeedback.
evidence-based assessment: an evaluation of the client using instruments that are reliable, valid, and possess clinical utility.
focal slowing (FS): slow-wave activity, typically delta (1-4 Hz) or theta (4-7 Hz), confined to one brain region and indicating localized cerebral dysfunction.
functional medicine: a medical approach that focuses on identifying and addressing the root causes of disease.
gamma rhythm: EEG activity from 30 to <80 Hz under the tutorial's working convention, associated with local cortical processing and vulnerable to muscle artifact.
generalization: the extension of a learned self-regulation skill beyond the training session to new settings, tasks, and times.
glyphosate: a common herbicide used to kill weeds, known to have potential health effects.
hertz (Hz): the SI unit of frequency equal to one cycle per second.
high beta: the upper portion of the beta band, most often defined as roughly 20-30 Hz, with some normative databases using a narrower 25-30 Hz band. Elevations are associated with hyperarousal, anxiety, rumination, and worry, and may also reflect EMG artifact.
infra-low frequency (ILF) training: neurofeedback that feeds back very slow fluctuations of the EEG signal, typically below 0.1 Hz, using continuous rather than threshold-based feedback.
interoception: the sensing and perception of internal bodily states; in neurofeedback learning, growing awareness of how a target brain state feels may come to guide self-regulation.
isolated epileptiform discharges (IEDs): brief, abnormal, paroxysmal spikes or sharp waves that stand out from the background EEG, typically last less than a second, and occur singly in people without clinical seizures.
local loops: neighboring cortical macrocolumns that share input and fire synchronously to generate frequencies above 30 Hz in the high-beta and gamma ranges.
local synchrony: synchrony that occurs when the coordinated firing of cortical neurons produces high-amplitude EEG signals.
low-resolution electromagnetic tomography (LORETA): the inverse solution of Pascual-Marqui and colleagues (1994) that estimates three-dimensional cortical sources of scalp-recorded EEG at low spatial resolution.
microbiome: the microorganisms in a defined habitat together with their genomes, products, and ecological context.
module: a cluster of nodes in a neural network that are more densely interconnected with each other than with nodes outside the cluster.
MTHFR gene: a gene that encodes the enzyme methylenetetrahydrofolate reductase, which is crucial for processing amino acids, particularly homocysteine, into methionine, impacting methylation and folate metabolism.
negative slow cortical potential: a slow negative cortical voltage shift commonly associated with increased cortical excitability and preparation for processing or action.
network node: an entity represented as a vertex in a graph and connected to other vertices by edges.
neural network: a system of interconnected ensembles of neurons that collaborate to achieve a goal.
non-learner: a client who does not gain control of the trained EEG parameter despite adequate training; identifying non-learning early prompts changes in feedback, instructions, or protocol.
normative database: a reference set of EEG measures collected from healthy subjects across age ranges, against which an individual client's values are compared as z-scores.
operant conditioning: learning in which a behavior, including a pattern of brain activity, becomes more or less likely depending on the consequences that follow it; the core learning mechanism of neurofeedback.
optimal response frequency (ORF): in ILF training, the target frequency, adjusted according to client report, at which the client feels most calm, alert, and emotionally even.
positive slow cortical potential: a slow positive cortical voltage shift commonly associated with reduced cortical excitability.
post-reinforcement synchronization (PRS): a brief burst of alpha-like EEG synchronization, mainly over parieto-occipital cortex, that follows delivery of a reward; it has been linked to learning and is one argument for including discrete reward events in feedback.
proportional feedback: feedback that varies continuously with the trained EEG parameter, such as a bar graph, a tone whose pitch tracks amplitude, or a video that brightens and dims, so the client receives information about every level of performance.
quantitative EEG (qEEG): the numerical analysis of digitized EEG features, such as spectral power, asymmetry, and connectivity, sometimes compared with normative databases; no universal minimum channel count defines it.
reinforcement latency: the delay between a target response and the feedback or reward that follows it; latencies longer than about 250-350 ms may weaken neurofeedback learning.
sensorimotor rhythm (SMR): a 12 to 15 Hz rhythm recorded over sensorimotor cortex, enhanced during physical stillness and attenuated by movement; it is defined topographically and behaviorally, so its range overlaps the mu and beta bands.
shaping: reinforcing successive approximations of a target response, typically by adjusting reward thresholds in planned steps.
slow cortical potential (SCP): a very slow EEG voltage shift lasting hundreds of milliseconds to seconds and reflecting changes in cortical excitability and preparation.
slow cortical potential training: neurofeedback that trains voluntary production of negative and positive slow cortical shifts associated with changes in cortical excitability.
spindling excessive beta (SEB): an EEG pattern of fast beta activity with a spindle-like appearance and an anterior emphasis, with a reported mean frequency of 20.6 Hz (SD = 4.1 Hz) spanning roughly 14-30 Hz.
swLORETA: a version of sLORETA that adds a singular-value-decomposition-based lead-field weighting, improving localization under realistic noise and for deep sources (Palmero-Soler et al., 2007).
theta/beta neurofeedback: a neurofeedback protocol that typically inhibits selected theta activity while reinforcing beta or sensorimotor-rhythm activity; parameters and evidence vary.
theta/beta ratio (TBR): EEG theta-band power divided by beta-band power using explicitly stated bands, electrodes, reference, and processing methods; it is not a diagnostic test for ADHD.
transfer trial: a training trial in which real-time feedback is withheld and the client attempts to produce the target state, learning only whether the attempt succeeded; used to promote generalization to daily life.
Wernicke's area: the area of the temporoparietal cortex (BA 22) of the dominant hemisphere specialized for speech comprehension. Damage can result in an inability to understand the meaning of speech and construct intelligible sentences.
z-score training: a neurofeedback approach using standardized deviations from a reference database to guide feedback; thresholds such as ±2 SD are protocol choices, not universal criteria.
References
Alkoby, O., Abu-Rmileh, A., Shriki, O., & Todder, D. (2018). Can we predict who will respond to neurofeedback? A review of the inefficacy problem and existing predictors for successful EEG neurofeedback learning. Neuroscience, 378, 155-164. https://doi.org/10.1016/j.neuroscience.2016.12.050
Amzica, F., & Lopes da Silva, F. H. (2018). Cellular substrates of brain rhythms. In D. L. Schomer & F. H. Lopes da Silva (Eds.), Niedermeyer's electroencephalography: Basic principles, clinical applications, and related fields (7th ed.). Oxford University Press.
Anderson, J. S. (1995). Program evaluation: EEG neurofeedback, New Visions School 1994-95 [Unpublished program report]. A Chance to Grow/New Visions School, Minneapolis, MN.
Anderson, J. S. (1996). Program evaluation: EEG neurofeedback, New Visions School 1995-96 [Unpublished program report]. A Chance to Grow/New Visions School, Minneapolis, MN.
Anderson, J. S. (1997). EEG neurofeedback annual report, New Visions School 1996-97 [Unpublished program report]. A Chance to Grow/New Visions School, Minneapolis, MN.
Anderson, J. S. (1998). EEG neurofeedback annual report, New Visions School 1997-98 [Unpublished program report]. A Chance to Grow/New Visions School, Minneapolis, MN.
Arnold, L. E., Arns, M., Barterian, J., Bergman, R., Black, S., Conners, C. K., Connor, S., Dasgupta, S., deBeus, R., Higgins, T., Hirshberg, L., Hollway, J. A., Kerson, C., Lightstone, H., Lofthouse, N., Lubar, J., McBurnett, K., Monastra, V., Buchan-Page, K., . . . Williams, C. E. (2021). Double-blind placebo-controlled randomized clinical trial of neurofeedback for attention-deficit/hyperactivity disorder with 13-month follow-up. Journal of the American Academy of Child & Adolescent Psychiatry, 60(7), 841-855. https://doi.org/10.1016/j.jaac.2020.07.906
Arns, M., Clark, C. R., Trullinger, M., deBeus, R., Mack, M., & Aniftos, M. (2020). Neurofeedback and attention-deficit/hyperactivity-disorder (ADHD) in children: Rating the evidence and proposed guidelines. Applied Psychophysiology and Biofeedback, 45(2), 39-48. https://doi.org/10.1007/s10484-020-09455-2
Breedlove, S. M., & Watson, N. V. (2020). Behavioral neuroscience (9th ed.). Sinauer Associates, Inc.
Cohen Kadosh, K., & Staunton, G. (2019). A systematic review of the psychological factors that influence neurofeedback learning outcomes. NeuroImage, 185, 545-555. https://doi.org/10.1016/j.neuroimage.2018.10.021
Collura, T. F. (2014). Technical foundations of neurofeedback. Taylor & Francis.
Davelaar, E. J. (2018). Mechanisms of neurofeedback: A computation-theoretic approach. Neuroscience, 378, 175-188. https://doi.org/10.1016/j.neuroscience.2017.05.052
Demos, J. N. (2019). Getting started with neurofeedback (2nd ed.). W. W. Norton & Company.
Fitts, P. M., & Posner, M. I. (1967). Human performance. Brooks/Cole.
Fokina, Yu. O., Kulichenko, A. M., & Pavlenko, V. B. (2010). Changes in the power levels of cortical EEG rhythms in cats during training using acoustic feedback signals. Neuroscience and Behavioral Physiology, 40(9), 951-954. https://doi.org/10.1007/s11055-010-9351-z
Gollan, J. K., Hoxha, D., Chihade, D., Pflieger, M. E., Rosebrock, L., & Cacioppo, J. (2014). Frontal alpha EEG asymmetry before and after behavioral activation treatment for depression. Biological Psychology, 99, 198-208. https://doi.org/10.1016/j.biopsycho.2014.03.003
Hallschmid, M., Mölle, M., Fischer, S., & Born, J. (2002). EEG synchronization upon reward in man. Clinical Neurophysiology, 113(7), 1059-1065. https://doi.org/10.1016/S1388-2457(02)00142-6
Herbet, G., & Duffau, H. (2020). Revisiting the functional anatomy of the human brain: Toward a meta-networking theory of cerebral functions. Physiological Reviews, 100, 1181-1228. https://doi.org/10.1152/physrev.00033.2019
Hirsch, E. (2020). Horses and zebras: Probabilities, uncertainty, and cognitive bias in clinical diagnosis. American Journal of Obstetrics and Gynecology, 222(5), 469.e1-469.e3. https://doi.org/10.1016/j.ajog.2020.01.010
Jaeschke, R., Guyatt, G. H., & Sackett, D. L. (1994). Users' guides to the medical literature: III. How to use an article about a diagnostic test. B. What are the results and will they help me in caring for my patients? JAMA, 271(9), 703-707. https://doi.org/10.1001/jama.1994.03510330081039
Kahneman, D. (2011). Thinking, fast and slow. Farrar, Straus and Giroux.
Kaiser, D. A. (2008). Functional connectivity and aging: Comodulation and coherence differences. Journal of Neurotherapy, 12, 123-139. https://doi.org/10.1080/10874200802398790
Kaiser, D. A., & Othmer, S. (2000). Effect of neurofeedback on variables of attention in a large multi-center trial. Journal of Neurotherapy, 4(1), 5-15. https://doi.org/10.1300/J184v04n01_02
Kerson, C., Sherlin, L. H., & Davelaar, E. J. (2026). Neurofeedback, biofeedback, and basic learning theory: Revisiting the 2011 conceptual framework. Applied Psychophysiology and Biofeedback, 51(3), 477-489. https://doi.org/10.1007/s10484-025-09756-4
Khazan, I., Shaffer, F., Moss, D., Lyle, R., & Rosenthal, S. (Eds.). (2023). Evidence-based practice in biofeedback and neurofeedback (4th ed.). Association for Applied Psychophysiology and Biofeedback.
La Vaque, T. J., Hammond, D. C., Trudeau, D., Monastra, V., Perry, J., Lehrer, P., Matheson, D., & Sherman, R. (2002). Template for developing guidelines for the evaluation of the clinical efficacy of psychophysiological interventions. Applied Psychophysiology and Biofeedback, 27(4), 273-281.
Legarda, S. B., McMahon, D., Othmer, S., & Othmer, S. F. (2011). Clinical neurofeedback: Case studies, proposed mechanism, and implications for pediatric neurology practice. Journal of Child Neurology, 26(8), 1045-1051. https://doi.org/10.1177/0883073811405052
Marczynski, T. J., Harris, C. M., & Livezey, G. T. (1981). The magnitude of post-reinforcement EEG synchronization (PRS) in cats reflects learning ability. Brain Research, 204(1), 214-219. https://doi.org/10.1016/0006-8993(81)90667-3
Monastra, V. J., Lubar, J. F., & Linden, M. (2001). The development of a quantitative electroencephalographic scanning process for attention deficit-hyperactivity disorder: Reliability and validity studies. Neuropsychology, 15(1), 136-144. https://doi.org/10.1037/0894-4105.15.1.136
Monastra, V. J., Lubar, J. F., Linden, M., VanDeusen, P., Green, G., Wing, W., Phillips, A., & Fenger, T. N. (1999). Assessing attention deficit hyperactivity disorder via quantitative electroencephalography: An initial validation study. Neuropsychology, 13(3), 424-433. https://doi.org/10.1037/0894-4105.13.3.424
Nunez, P. L., & Srinivasan, R. (2006). Electric fields of the brain (2nd ed.). Oxford University Press.
Othmer, S. (2007, October 3). The self in self-regulation. EEG Info. https://news.eeginfo.com/the-self-in-self-regulation/
Othmer, S. (2010, March 10). Introduction to infra-low frequency training. EEG Info. https://news.eeginfo.com/introduction-to-infra-low-frequency-training/
Othmer, S. (2024, December 31). A revisionist view of neurofeedback. EEG Info. https://news.eeginfo.com/a-revisionist-view-of-neurofeedback/
Othmer, S., & Othmer, S. F. (2016). Infra-low-frequency neurofeedback for optimum performance. Biofeedback, 44(2), 81-89. https://doi.org/10.5298/1081-5937-44.2.07
Othmer, S., Othmer, S. F., Kaiser, D. A., & Putman, J. (2013). Endogenous neuromodulation at infralow frequencies. Seminars in Pediatric Neurology, 20(4), 246-257. https://doi.org/10.1016/j.spen.2013.10.006
Palmero-Soler, E., Dolan, K., Hadamschek, V., & Tass, P. A. (2007). swLORETA: A novel approach to robust source localization and synchronization tomography. Physics in Medicine and Biology, 52(7), 1783-1800.
Pascual-Marqui, R. D., Michel, C. M., & Lehmann, D. (1994). Low resolution electromagnetic tomography: A new method for localizing electrical activity in the brain. International Journal of Psychophysiology, 18(1), 49-65. https://doi.org/10.1016/0167-8760(84)90014-X
Ros, T., Enriquez-Geppert, S., Zotev, V., Young, K. D., Wood, G., Whitfield-Gabrieli, S., Wan, F., Vuilleumier, P., Vialatte, F., Van De Ville, D., Todder, D., Surmeli, T., Sulzer, J. S., Strehl, U., Sterman, M. B., Steiner, N. J., Sorger, B., Soekadar, S. R., Sitaram, R., . . . Thibault, R. T. (2020). Consensus on the reporting and experimental design of clinical and cognitive-behavioural neurofeedback studies (CRED-nf checklist). Brain, 143(6), 1674-1685. https://doi.org/10.1093/brain/awaa009
Sherlin, L. H., Arns, M., Lubar, J., Heinrich, H., Kerson, C., Strehl, U., & Sterman, M. B. (2011). Neurofeedback and basic learning theory: Implications for research and practice. Journal of Neurotherapy, 15(4), 292-304. https://doi.org/10.1080/10874208.2011.623089
Smith, C. S., & Paauw, D. S. (2000). When you hear hoof beats: Four principles for separating zebras from horses. The Journal of the American Board of Family Practice, 13(6), 424-429. https://doi.org/10.3122/15572625-13-6-424
Sollfrank, T., Ramsay, A., Perdikis, S., Williamson, J., Murray-Smith, R., Leeb, R., Millán, J. d. R., & Kübler, A. (2016). The effect of multimodal and enriched feedback on SMR-BCI performance. Clinical Neurophysiology, 127(1), 490-498. https://doi.org/10.1016/j.clinph.2015.06.004
Strehl, U. (2014). What learning theories can teach us in designing neurofeedback treatments. Frontiers in Human Neuroscience, 8, Article 894. https://doi.org/10.3389/fnhum.2014.00894
Swatzyna, R. J., Morrow, L. M., Collins, D. M., Barr, E. A., Roark, A. J., & Turner, R. P. (2024). Evidentiary significance of routine EEG in refractory cases: A paradigm shift in psychiatry. Clinical EEG and Neuroscience, 15500594231221313. Advance online publication. https://doi.org/10.1177/15500594231221313
Swingle, P. G. (2015). Adding neurofeedback to your practice: Clinician's guide to ClinicalQ, neurofeedback, and braindriving. Springer.
Tan, G., Shaffer, F., Lyle, R., & Teo, I. (Eds.). (2016). Evidence-based practice in biofeedback and neurofeedback (3rd ed.). Association for Applied Psychophysiology and Biofeedback.
Thatcher, R. W. (1998). Normative EEG databases and EEG biofeedback. Journal of Neurotherapy, 2(4), 8-39. https://doi.org/10.1300/J184v02n04_02
Thatcher, R. W., Lubar, J. F., & Koberda, J. L. (2019). Z-Score EEG biofeedback: Past, present, and future. Biofeedback, 47(4), 89-103. https://doi.org/10.5298/1081-5937-47.4.04
Thompson, M., & Thompson, L. (2015). The neurofeedback book: An introduction to basic concepts in applied psychophysiology (2nd ed.). Association for Applied Psychophysiology and Biofeedback.
Travis, T. A., Kondo, C. Y., & Knott, J. R. (1974). Parameters of eyes-closed alpha enhancement. Psychophysiology, 11(6), 674-681. https://doi.org/10.1111/j.1469-8986.1974.tb01136.x
Van Doren, J., Arns, M., Heinrich, H., Vollebregt, M. A., Strehl, U., & Loo, S. K. (2019). Sustained effects of neurofeedback in ADHD: A systematic review and meta-analysis. European Child & Adolescent Psychiatry, 28(3), 293-305. https://doi.org/10.1007/s00787-018-1121-4
Weber, L. A., Ethofer, T., & Ehlis, A.-C. (2020). Predictors of neurofeedback training outcome: A systematic review. NeuroImage: Clinical, 27, Article 102301. https://doi.org/10.1016/j.nicl.2020.102301
Yang, W., Yuan, J., Ding, L., & Chow, S. K. K. (2026). A neurofeedback-guided EEG and BCI framework for personalized attention rehabilitation in ADHD. Neuroscience, 602, 67-80. https://doi.org/10.1016/j.neuroscience.2026.03.010
Return to Top